Real reports translated from the Czech originals, with identifying details removed: history, technique, key findings, conclusion with differential diagnosis and recommendation. Each case also includes the version we use to explain it to the client.
Oncology, Abdomen, Head and neck
Right thyroid lobe mass and multisystemic findings in a cat treated for hyperthyroidism
Patient
cat, domestic shorthair, spayed female, 16 years
Examination
Whole-body CT, pre- and post-contrast
Date
March 2026
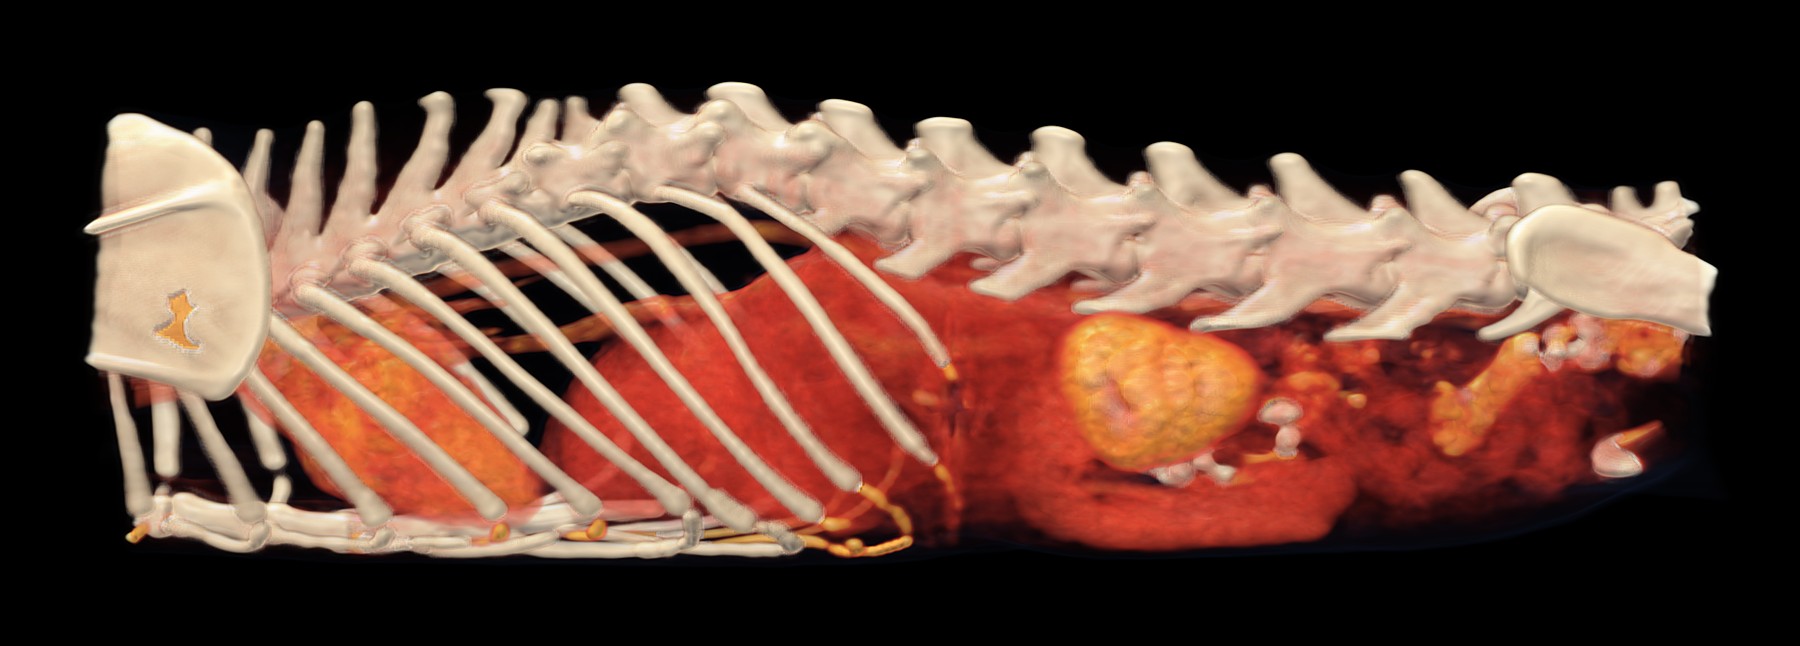
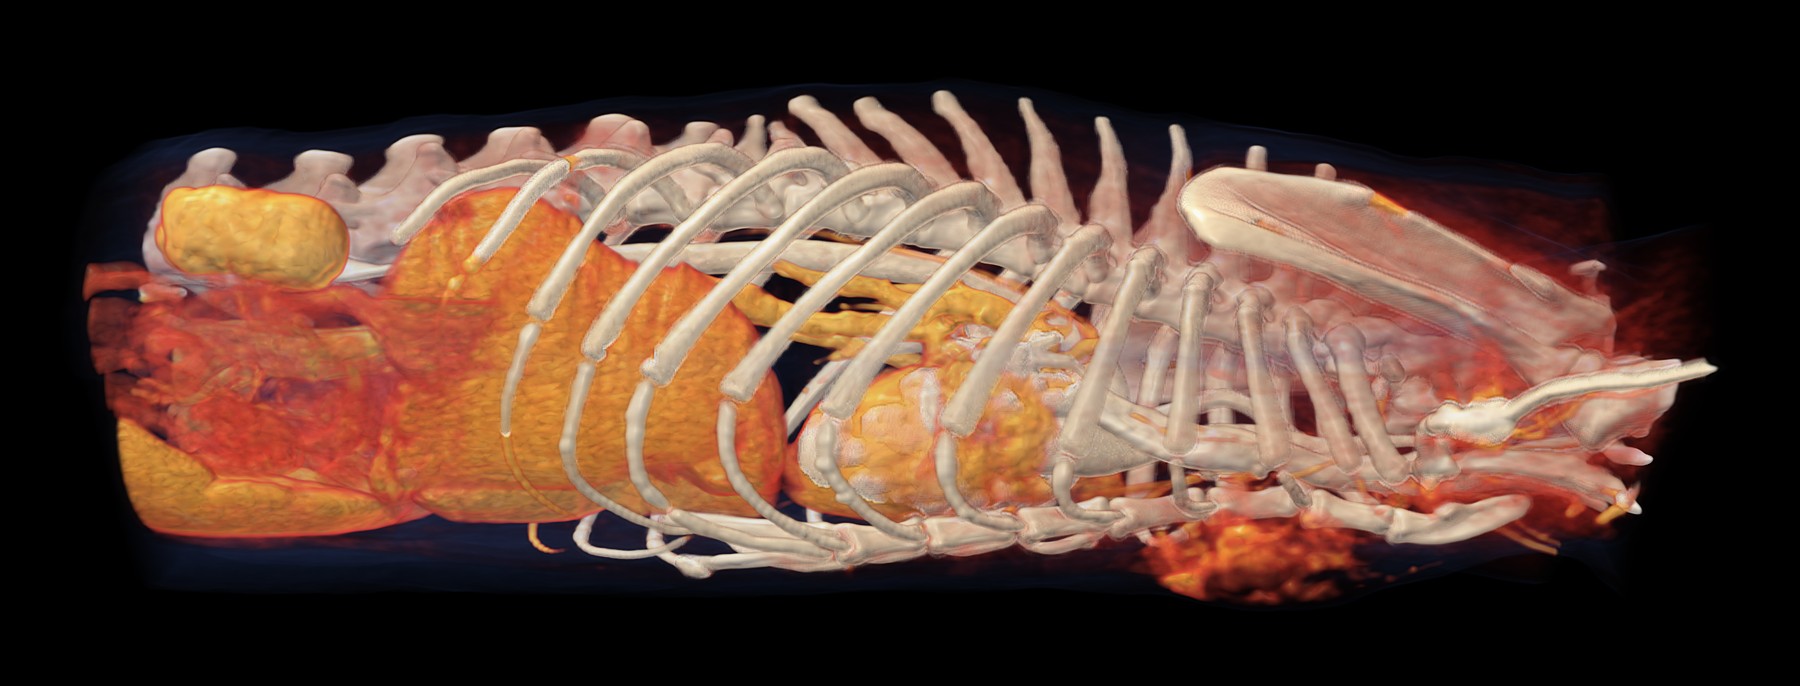
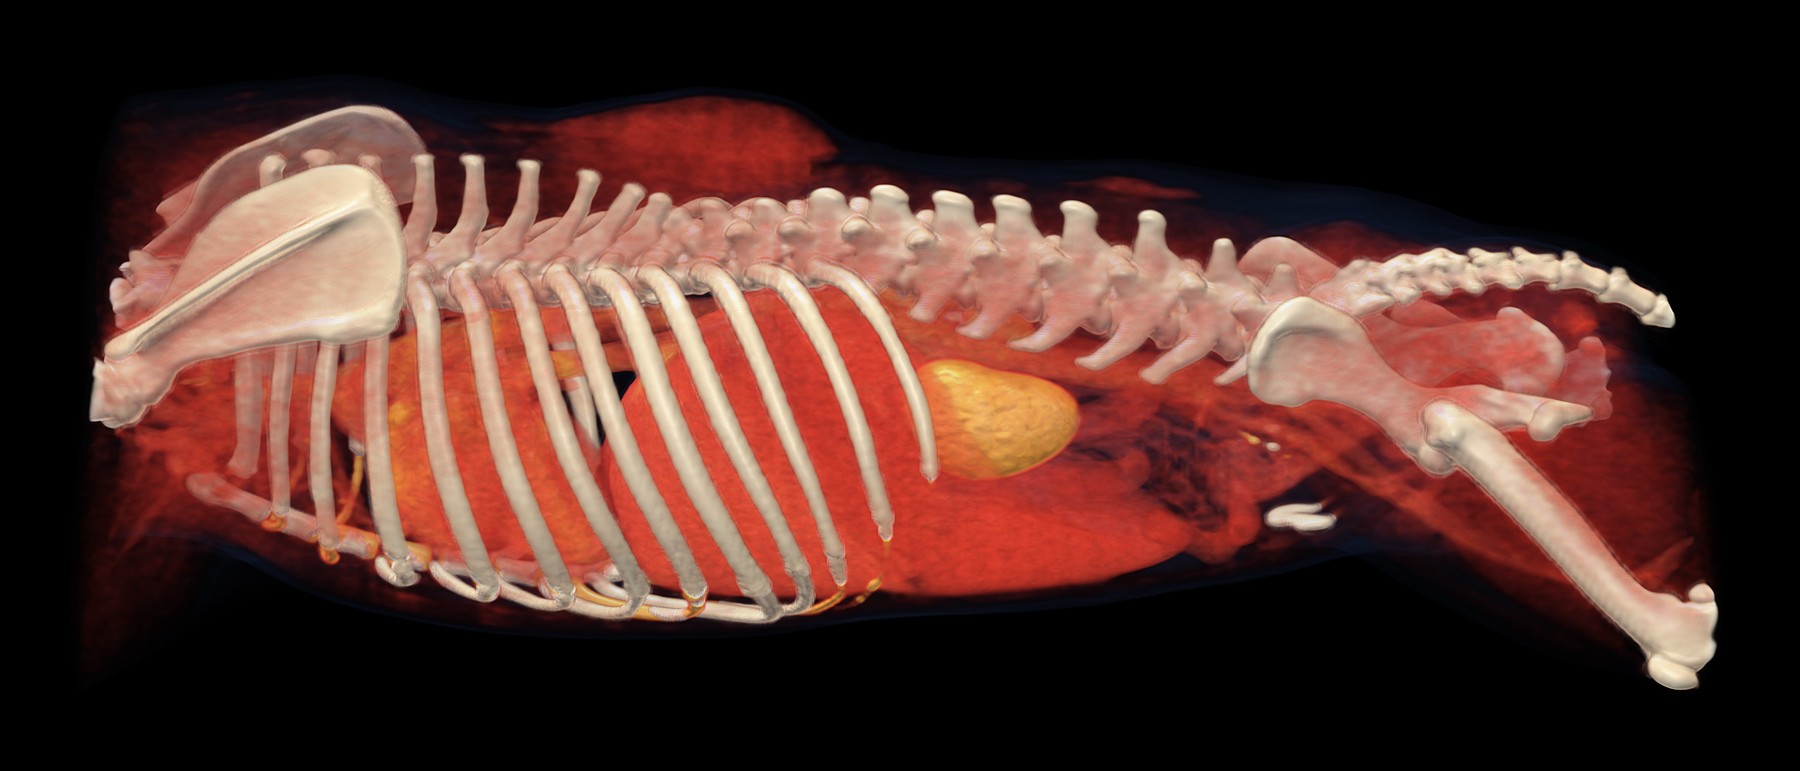
Volume rendering (VR) with an HU-based colour map from the 2 mm post-contrast series, resampled to an isotropic voxel size of 0.4 mm, left lateral view: enlarged left kidney with irregular contours, heart cranially.
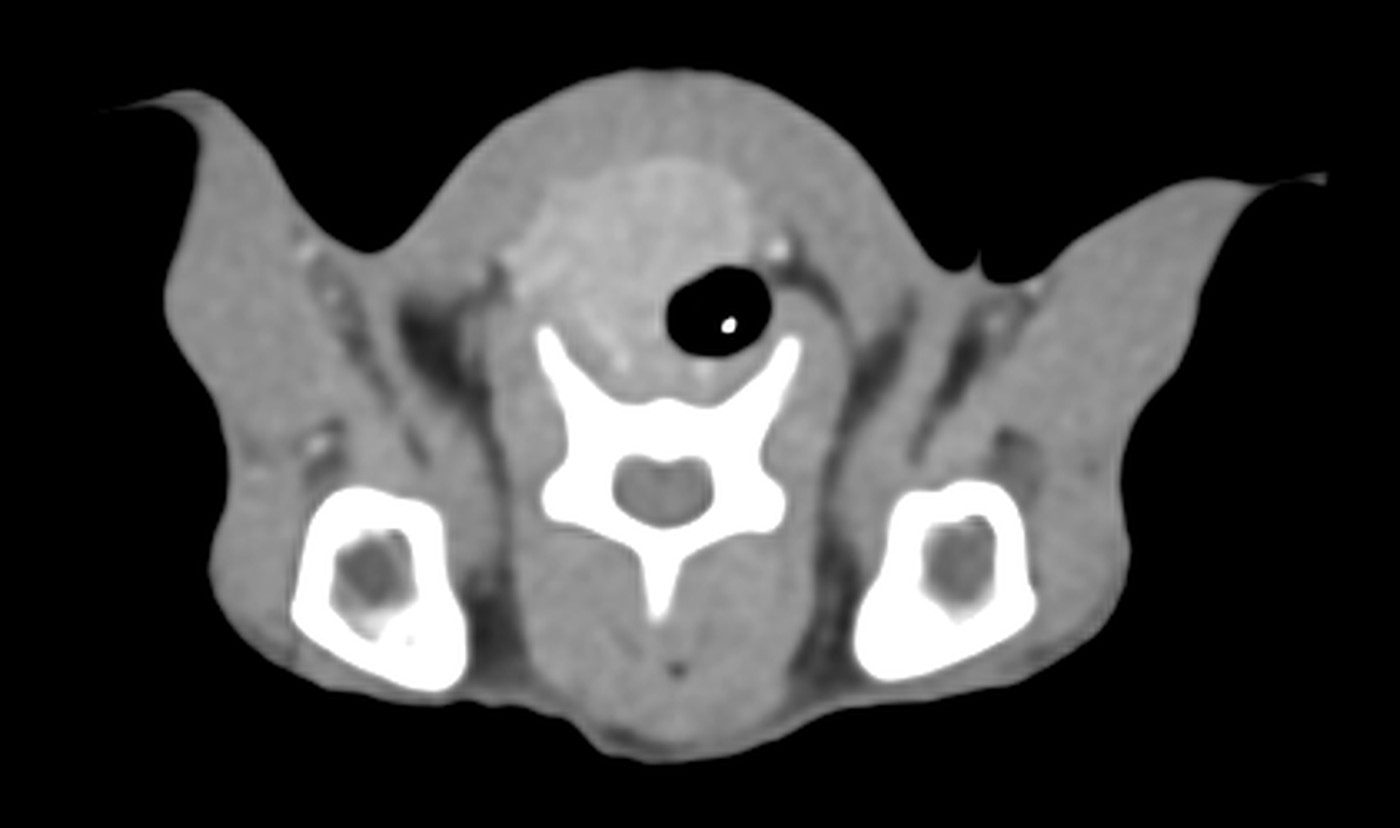
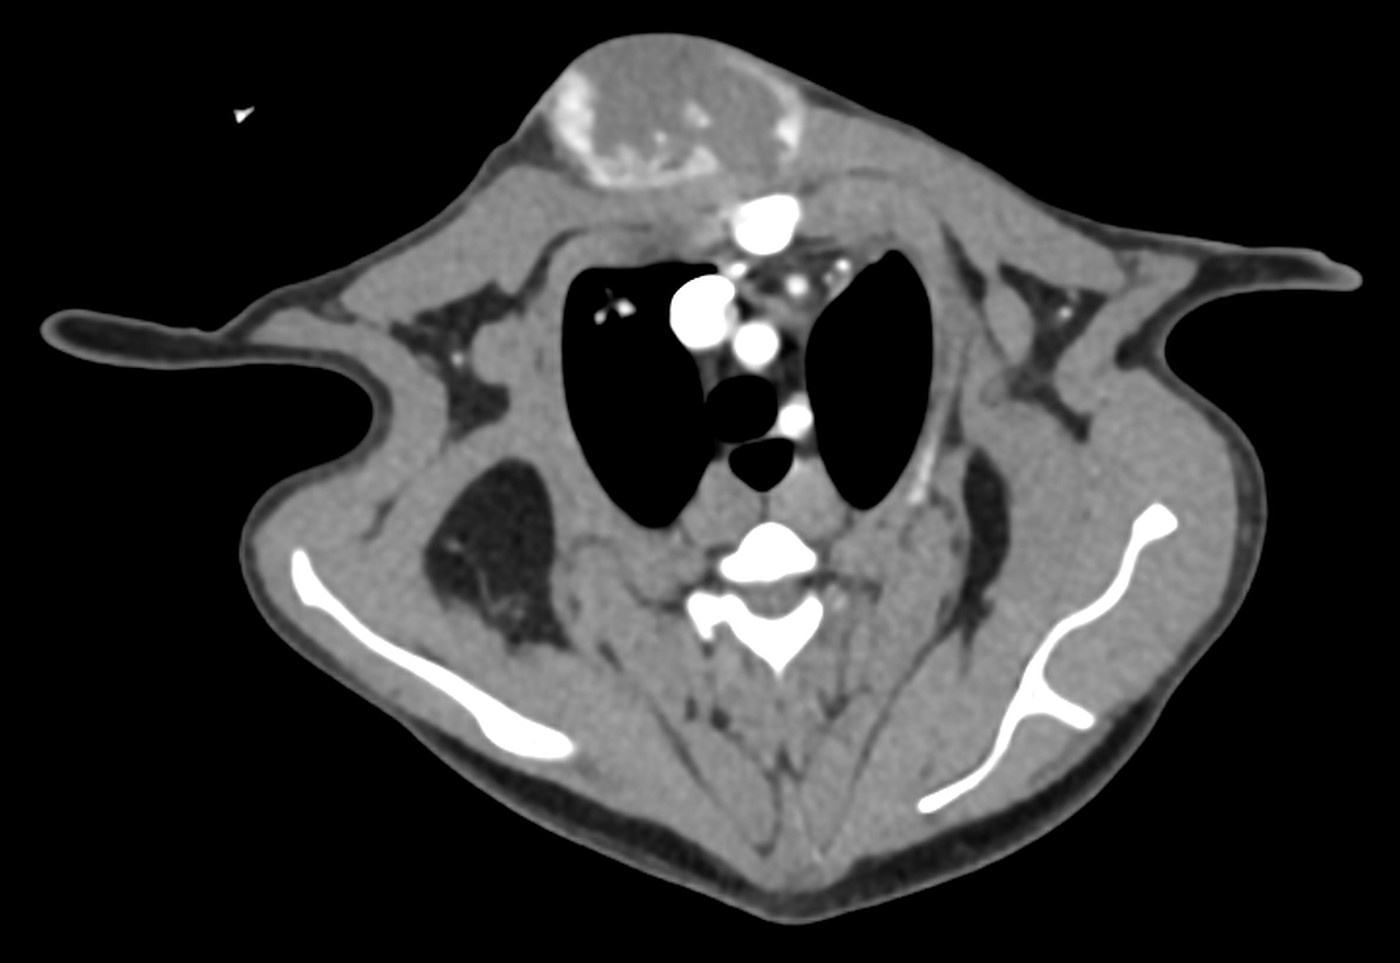
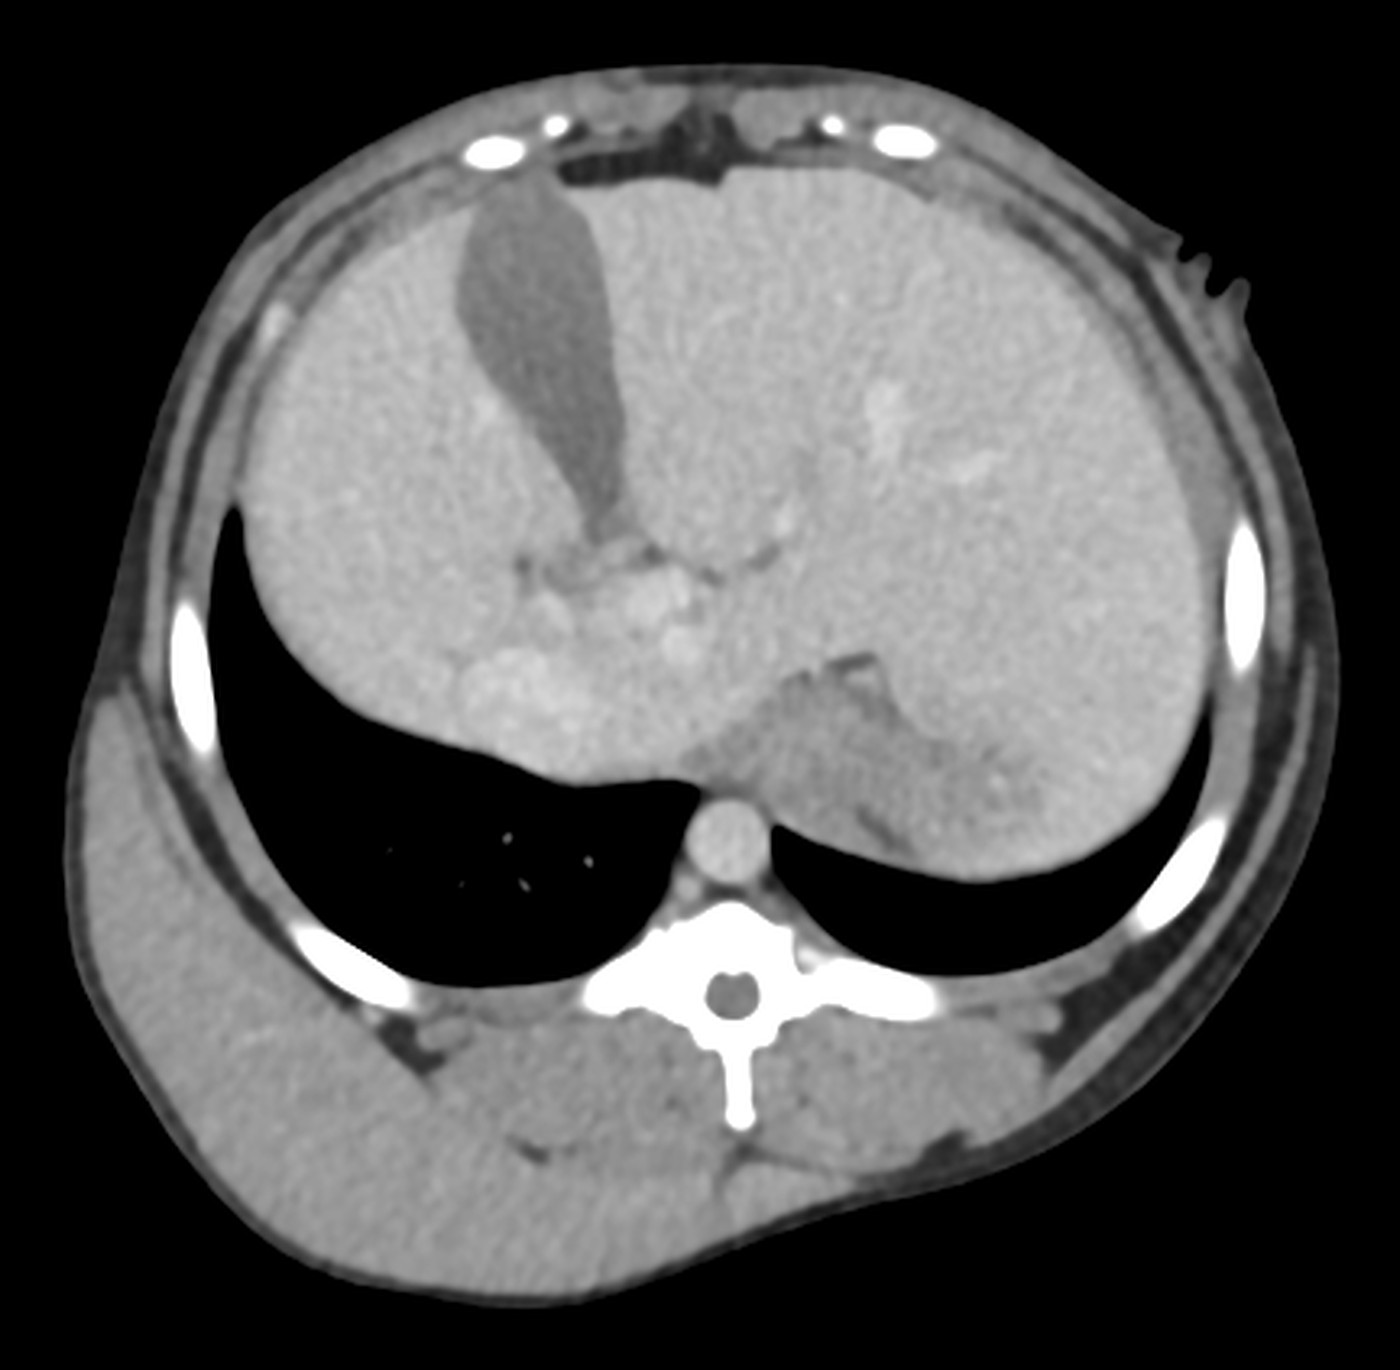
Transverse slice through the neck, post-contrast, soft tissue window W 400 / L 40: right thyroid lobe mass ventrolateral to the trachea.
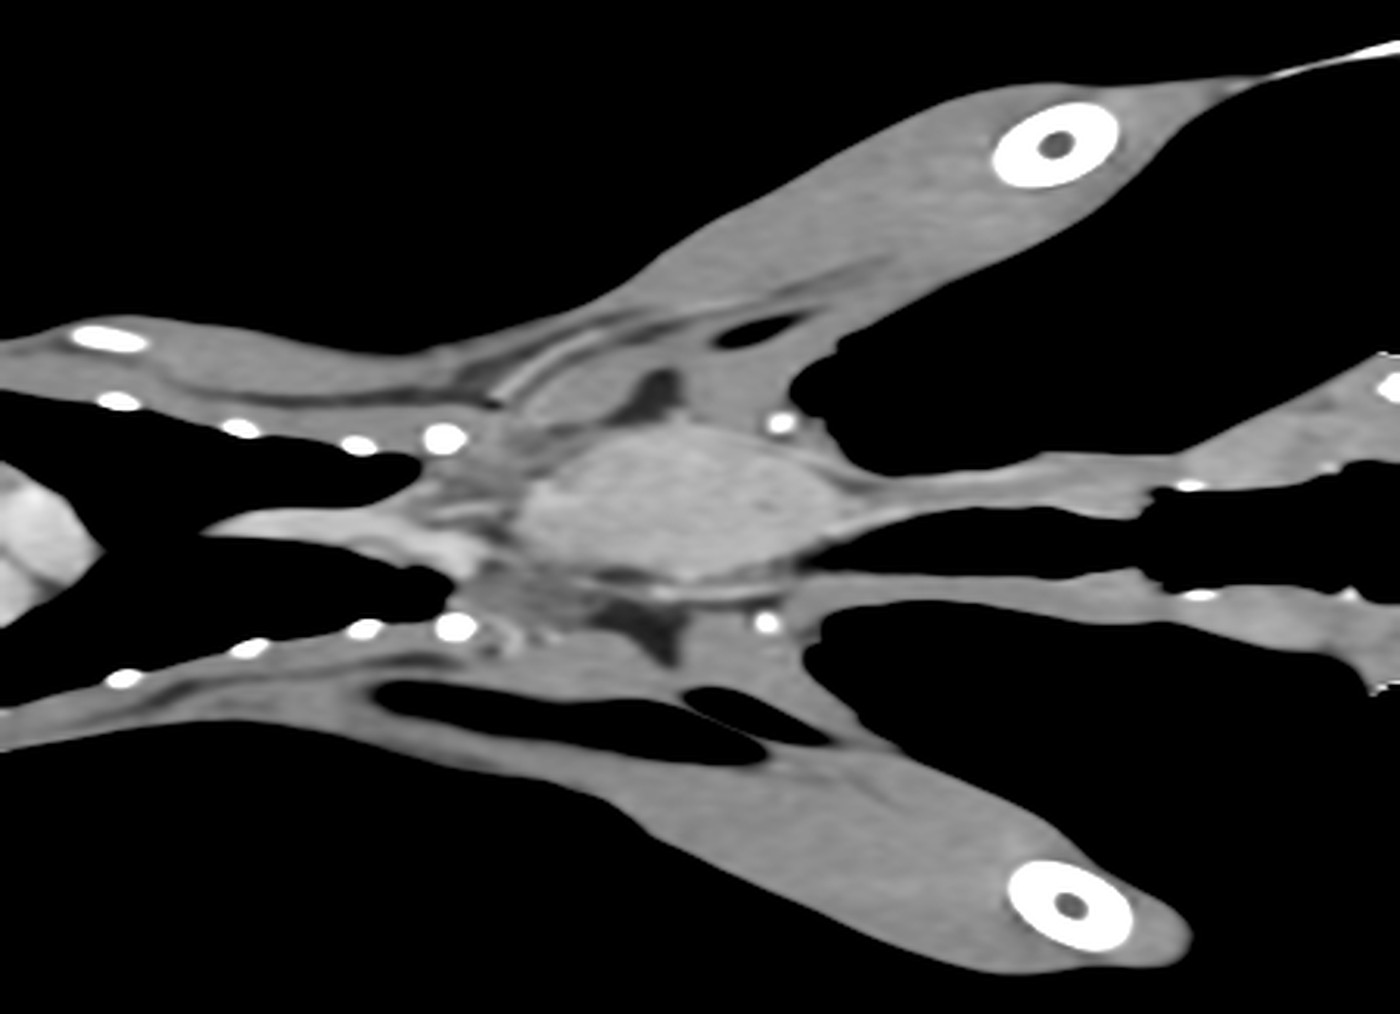
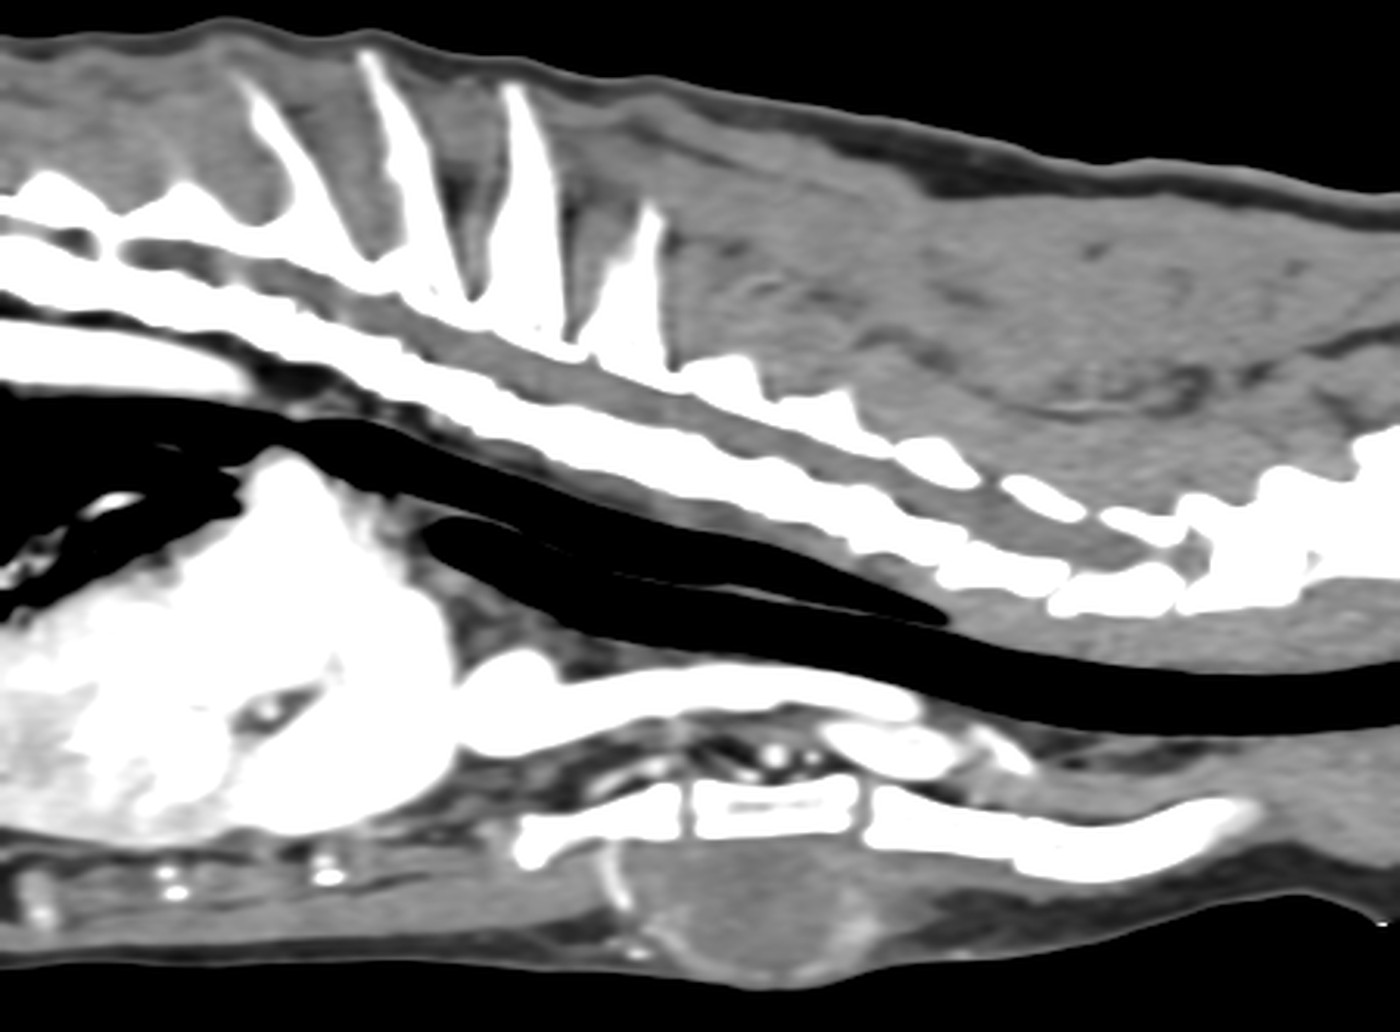
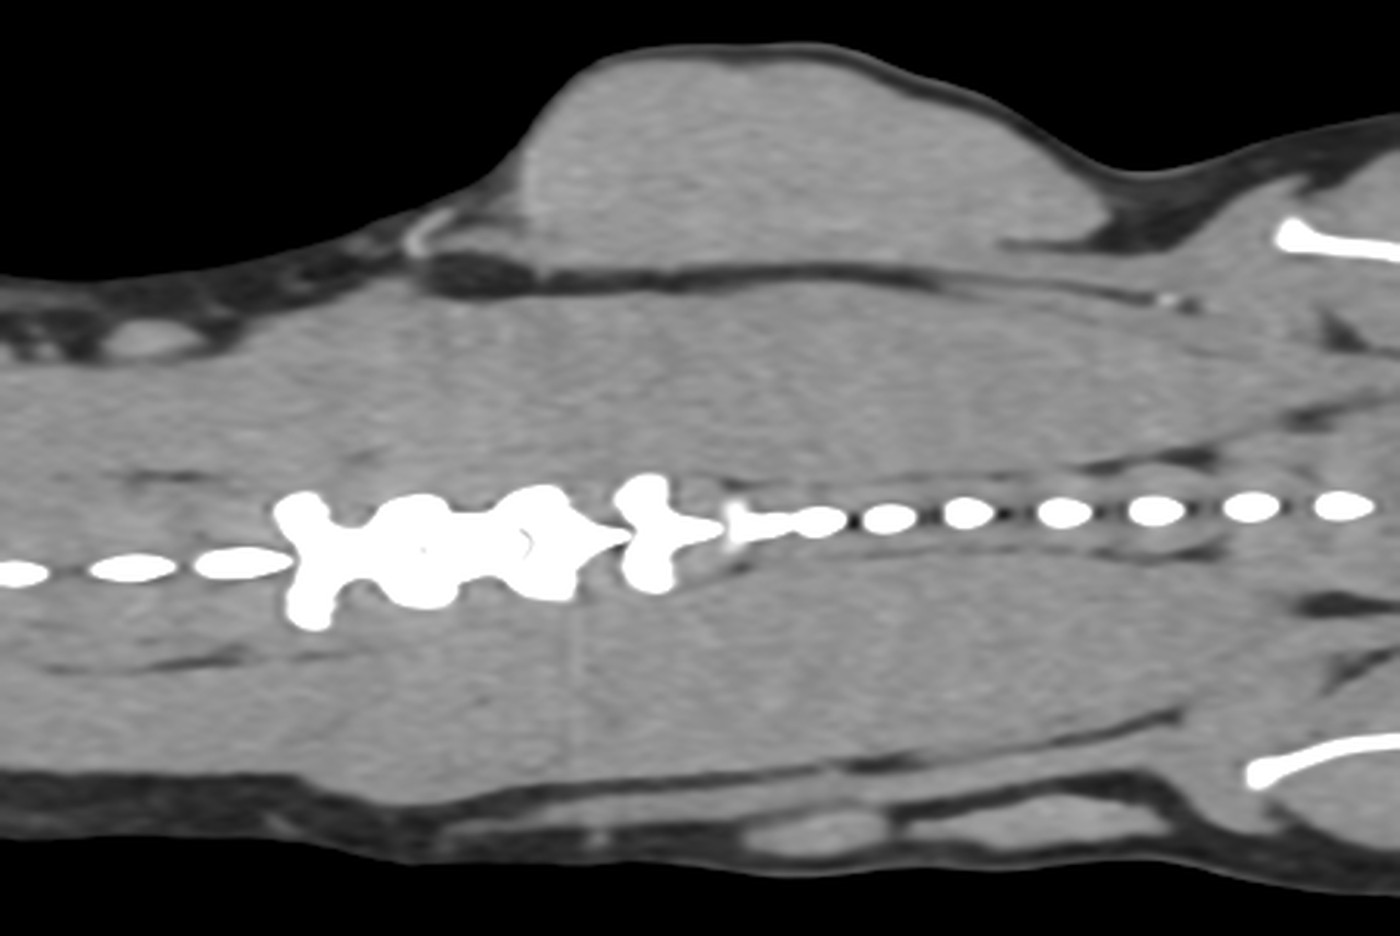
Dorsal plane through the neck at the level of the thyroid gland, post-contrast, W 400 / L 40: right thyroid lobe mass, approximately 4 cm in length.
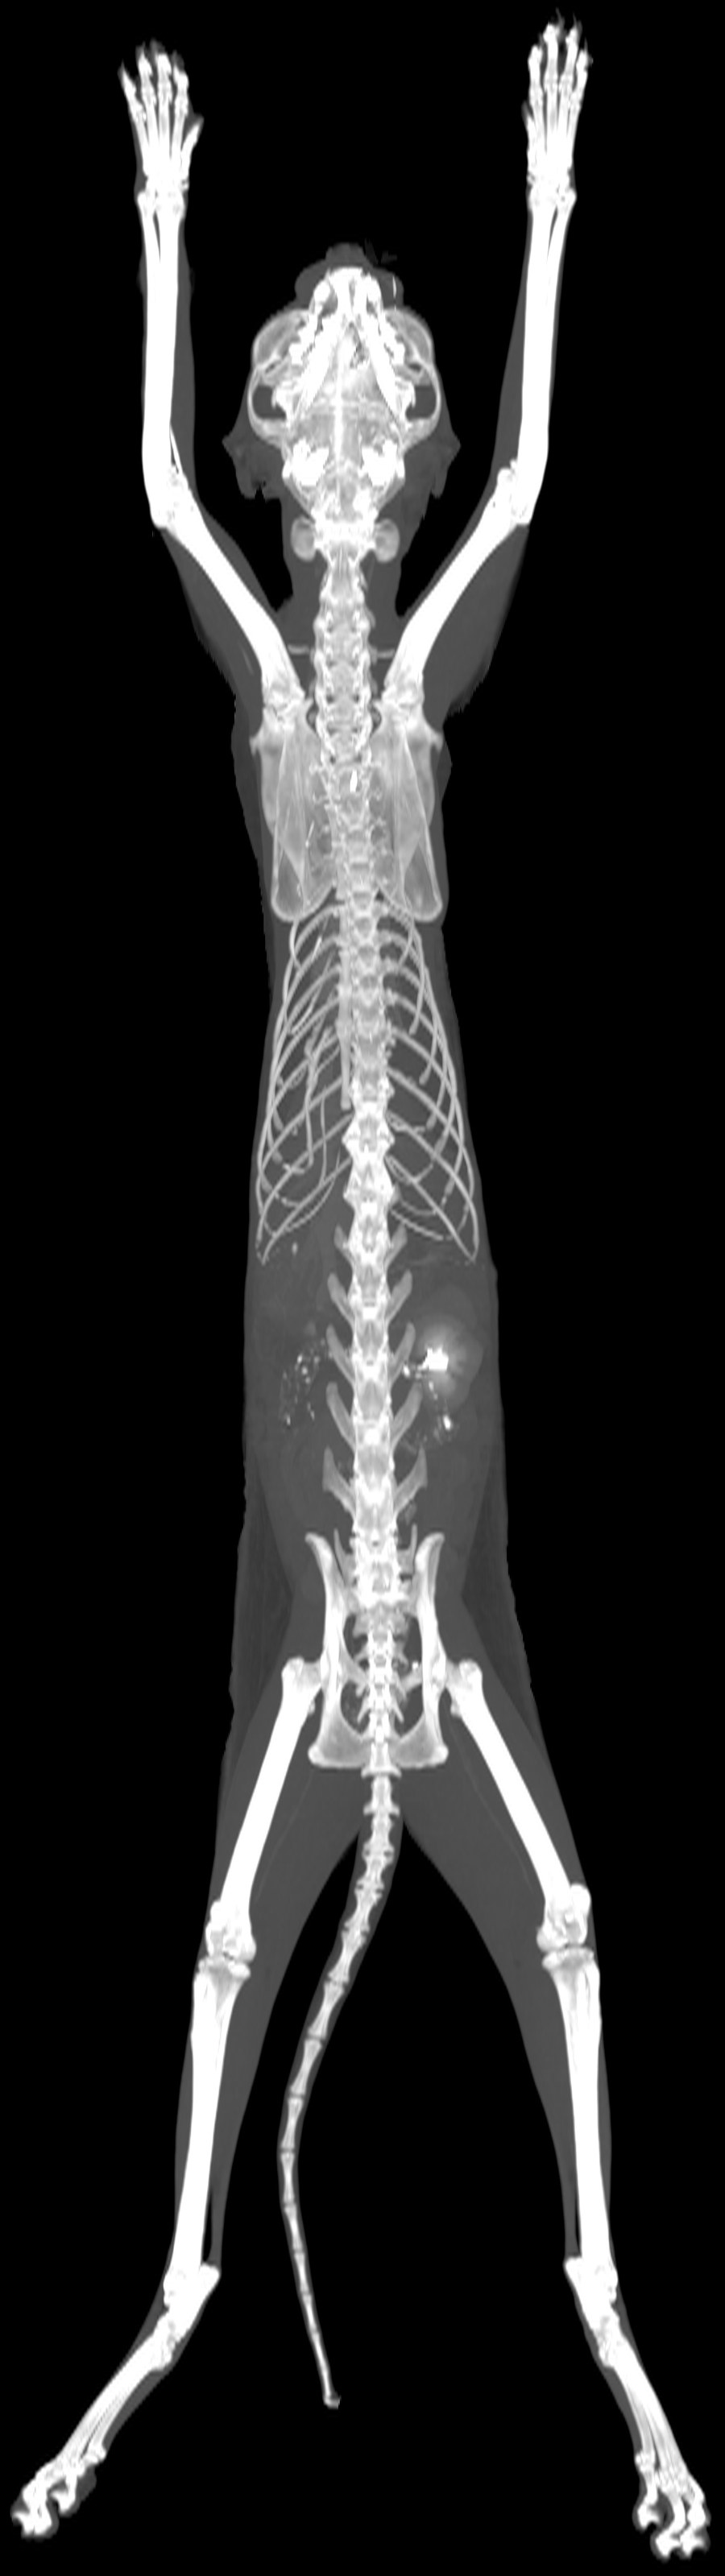
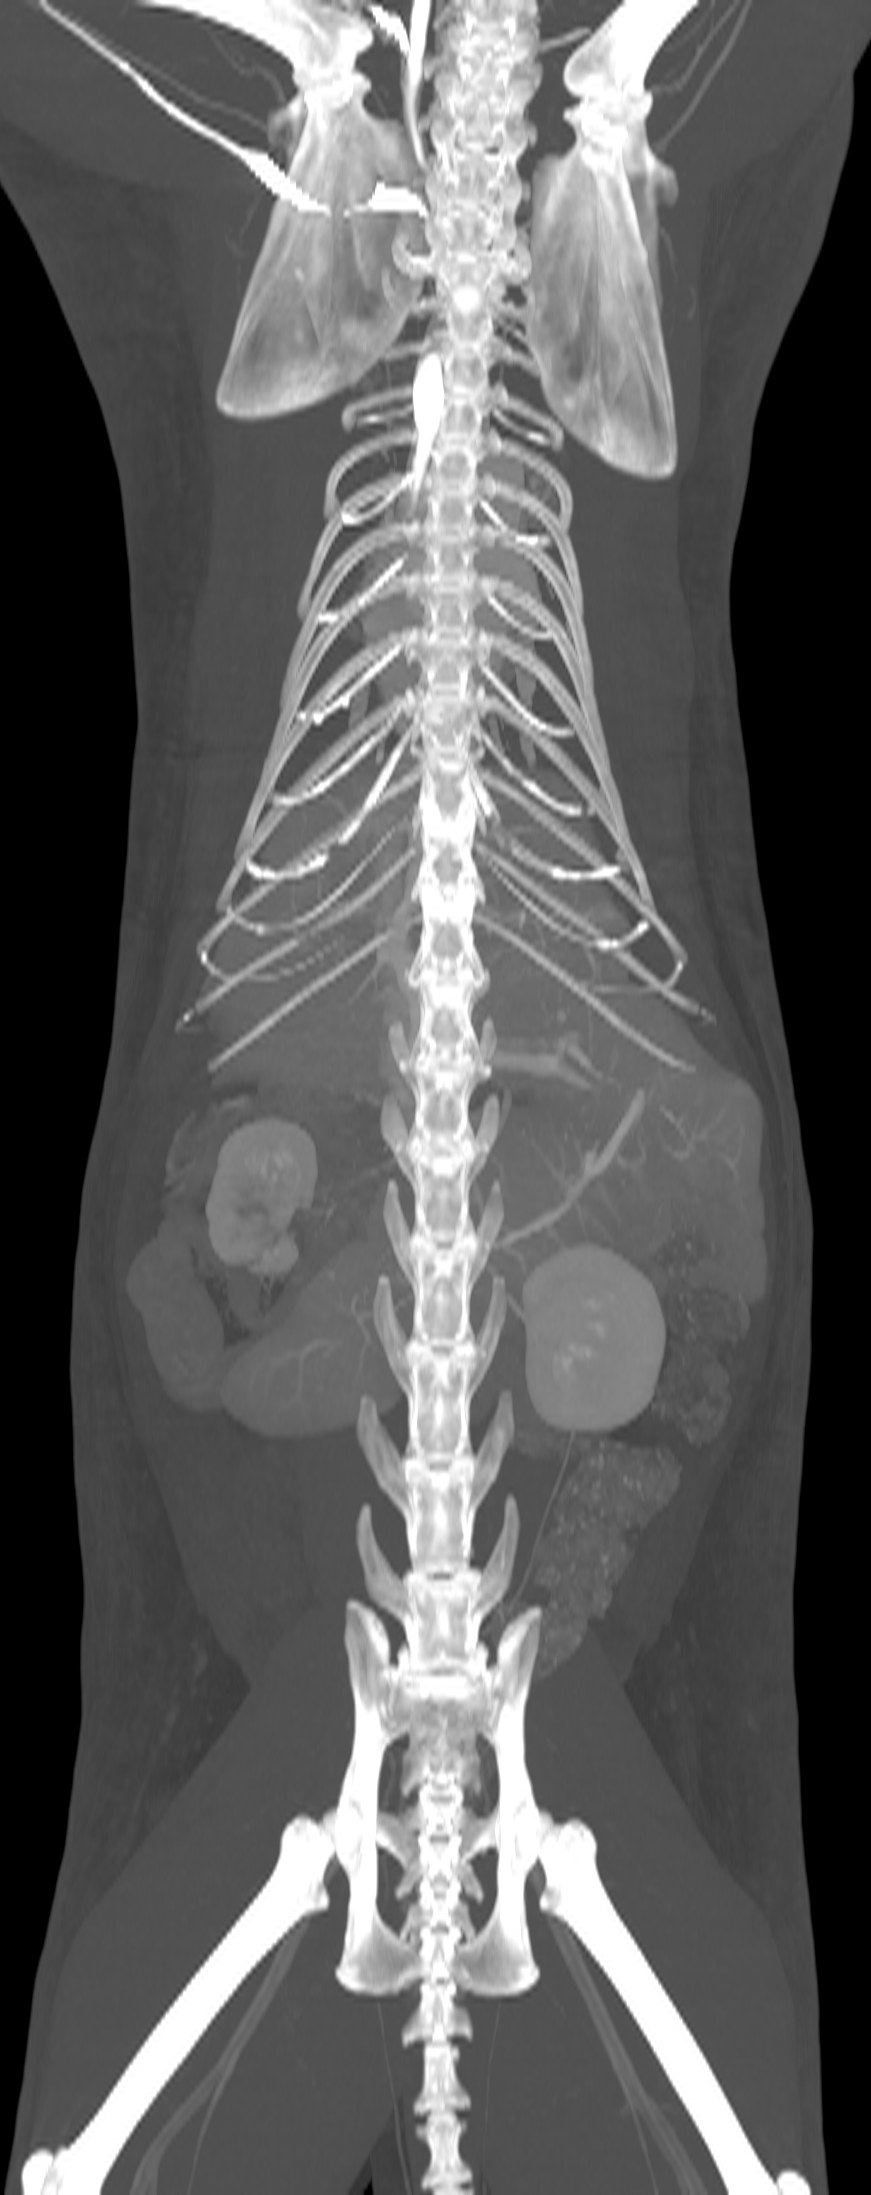
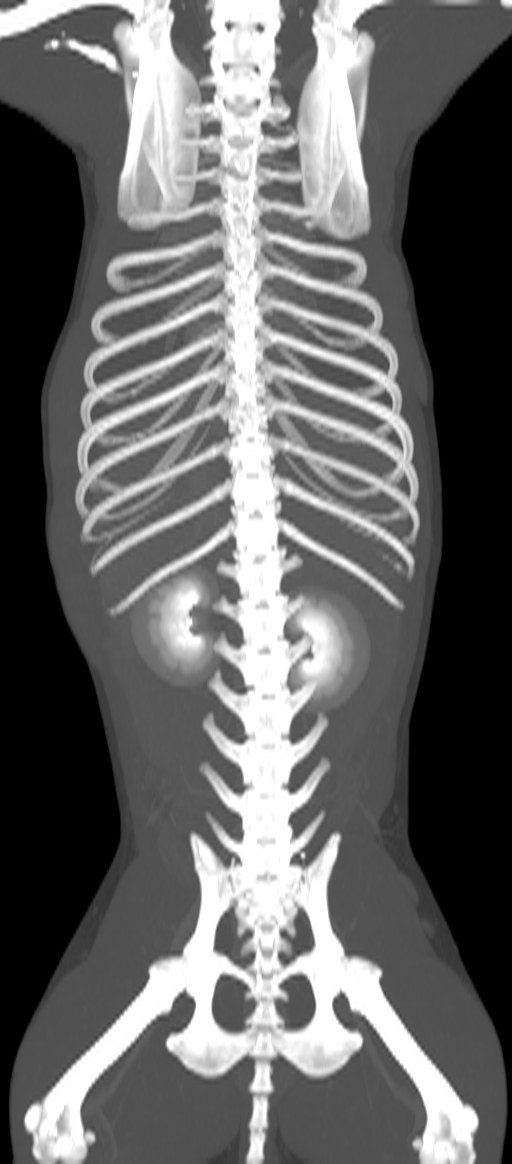
Dorsal MIP of the entire volume, post-contrast.
History
Cachexia, chronic haematemesis. Under treatment for hyperthyroidism.
Technique
4,056 slices (1 and 2 mm), pre- and post-contrast series reconstructed with medium- and high-frequency algorithms. Good study quality.
Findings
–Neck: oval, irregular mass of heterogeneous soft tissue attenuation, mildly hypoattenuating relative to the adjacent musculature, heterogeneously enhancing, located ventrally on the right, without vascular invasion or invasion of the surrounding tissues; corresponds to the right thyroid lobe (40.6 × 14.7 × 18.5 mm). Left lobe not identified.
–Thorax: enlarged sternal lymph nodes without a visible hilum. Left atrial dilatation; thickened left ventricular free wall and interventricular septum.
–Liver: hypoattenuating, non-enhancing nodular lesion in the right lateral lobe (5.5 × 7.3 × 7.8 mm); small lesion in the left medial lobe, isoattenuating on pre-contrast and hypoattenuating on post-contrast images (4.3 × 5 × 5.2 mm).
–Spleen: heterogeneous enhancement of the cranial margin; multiple irregularly shaped hypoattenuating foci.
–Kidneys: right kidney small and non-enhancing, with a triangular hyperattenuating focus at the level of the renal pelvis; left kidney enlarged, with irregular contours and heterogeneous enhancement, containing multiple oval to spherical hypoattenuating foci, some protruding beyond the renal contour.
–Stomach: diffuse circumferential wall thickening at the cardia and along the greater curvature, with homogeneous enhancement.
–Small intestine difficult to assess; multifocal fat stranding and adhesions between intestinal loops.
–Lymph nodes: enlarged gastric, splenic, cranial and caudal mesenteric, lumbar aortic, internal and medial iliac nodes, without a visible hilum.
–Peritoneum: fat stranding in the mesogastric and hypogastric regions; multifocal small volumes of free fluid.
–Ears: retention of a small amount of fluid in the right horizontal ear canal with mild thickening of its wall; multiple mineralised foci in the walls of both external ear canals (incidental dystrophic mineralisation or chronic otitis externa); reduced volume and thickened walls of both tympanic bullae, which contain material of fluid/soft tissue attenuation (common in brachycephalic dogs).
–Heart: irregular soft tissue attenuating mass at the heart base, heterogeneously enhancing, encircling the aorta, in contact with both the left and right atria and compressing the left and right pulmonary arteries (49 × 34.8 × 42.8 mm). Focal pericardial effusion on the left.
–Prostate: symmetrical, heterogeneously enhancing, with multiple small non-enhancing foci in the parenchyma.
–Pelvis: focal soft tissue thickening in the left ventral perianal region with peripheral enhancement.
–Skeleton: bilateral tarsal osteoproliferation; incomplete fusion of the ossification centres of the dorsal arch of the atlas; vertebral malformations typical of the breed.
Conclusion
–Grade 4 caudal aberrant turbinates.
–Bilateral otitis externa with accumulation of secretions in the right ear canal.
–Bilateral tympanic bulla changes consistent with a brachycephalic breed.
–Heart base mass. DDx: chemodectoma (aortic body neoplasia), haemangiosarcoma, neuroendocrine neoplasia.
Bilateral chylous pleural effusion with atelectasis; psoas minor thickening in a cat following excision of an adenocarcinoma
Patient
cat, domestic shorthair, spayed female, 9 years
Examination
Whole-body CT, pre- and post-contrast
Date
May 2026
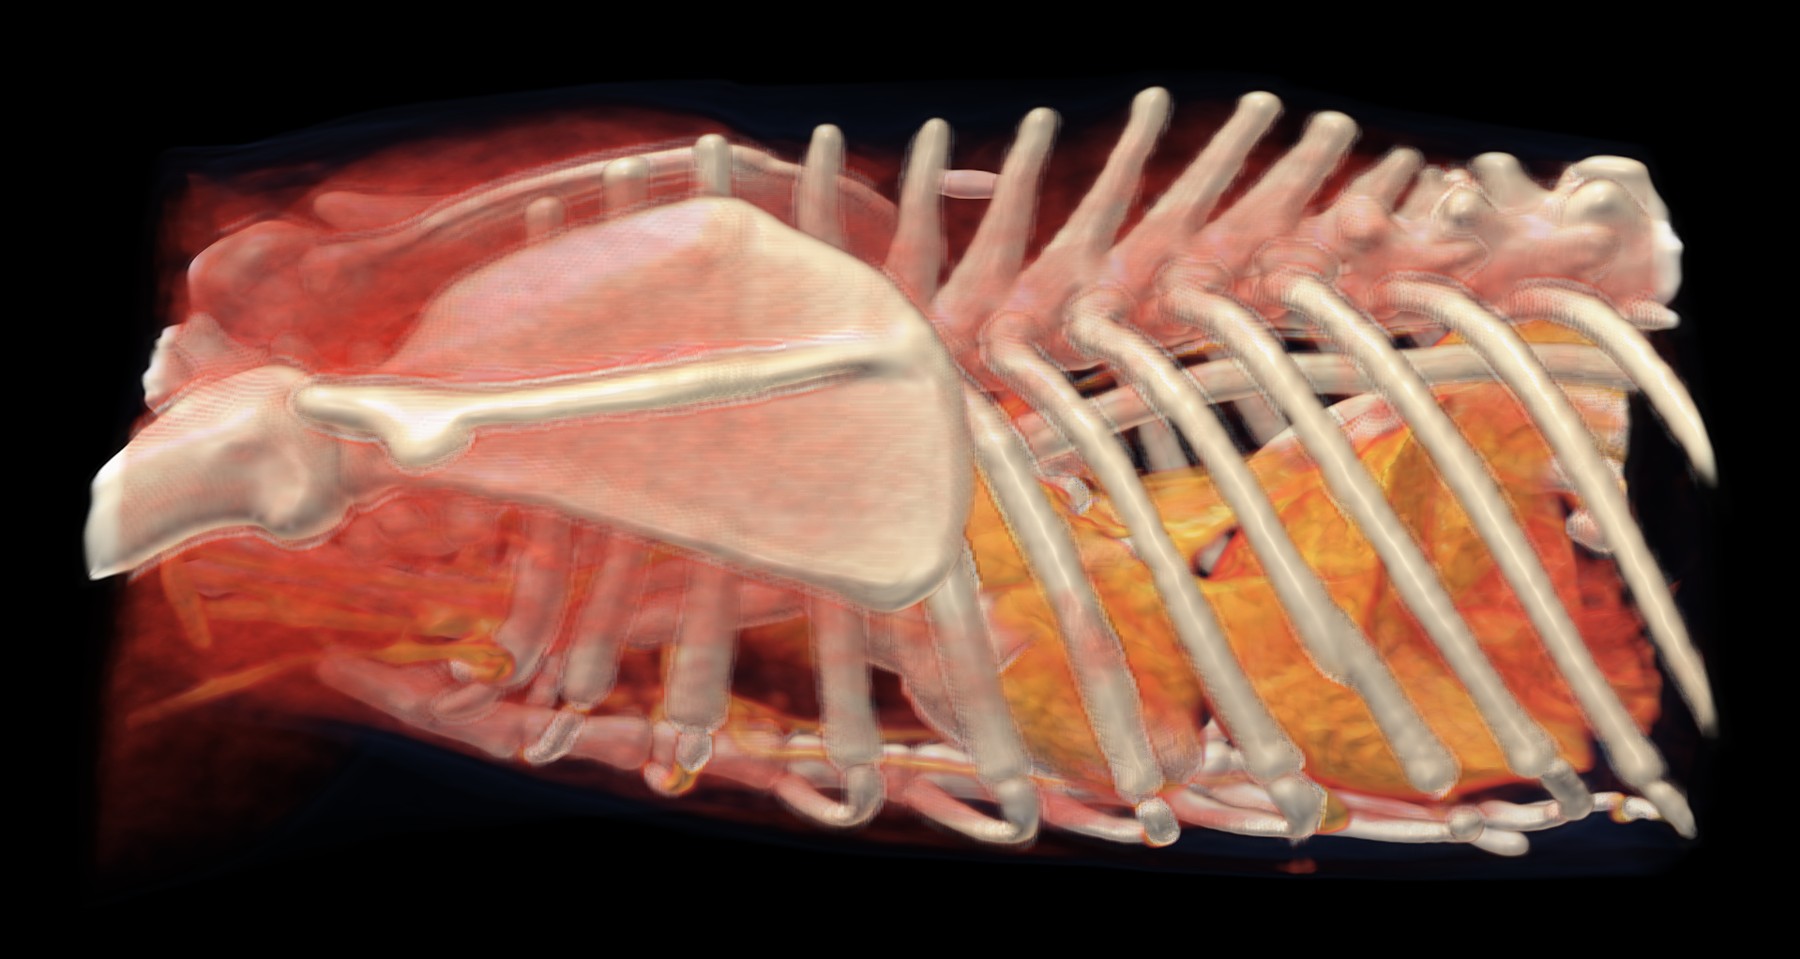
Volume rendering (VR) with an HU-based colour map from the 2 mm post-contrast series, resampled to an isotropic voxel size of 0.4 mm, left lateral view of the thorax. The pleural effusion is of fluid attenuation and is not displayed in VR; it is assessed on the transverse slices.
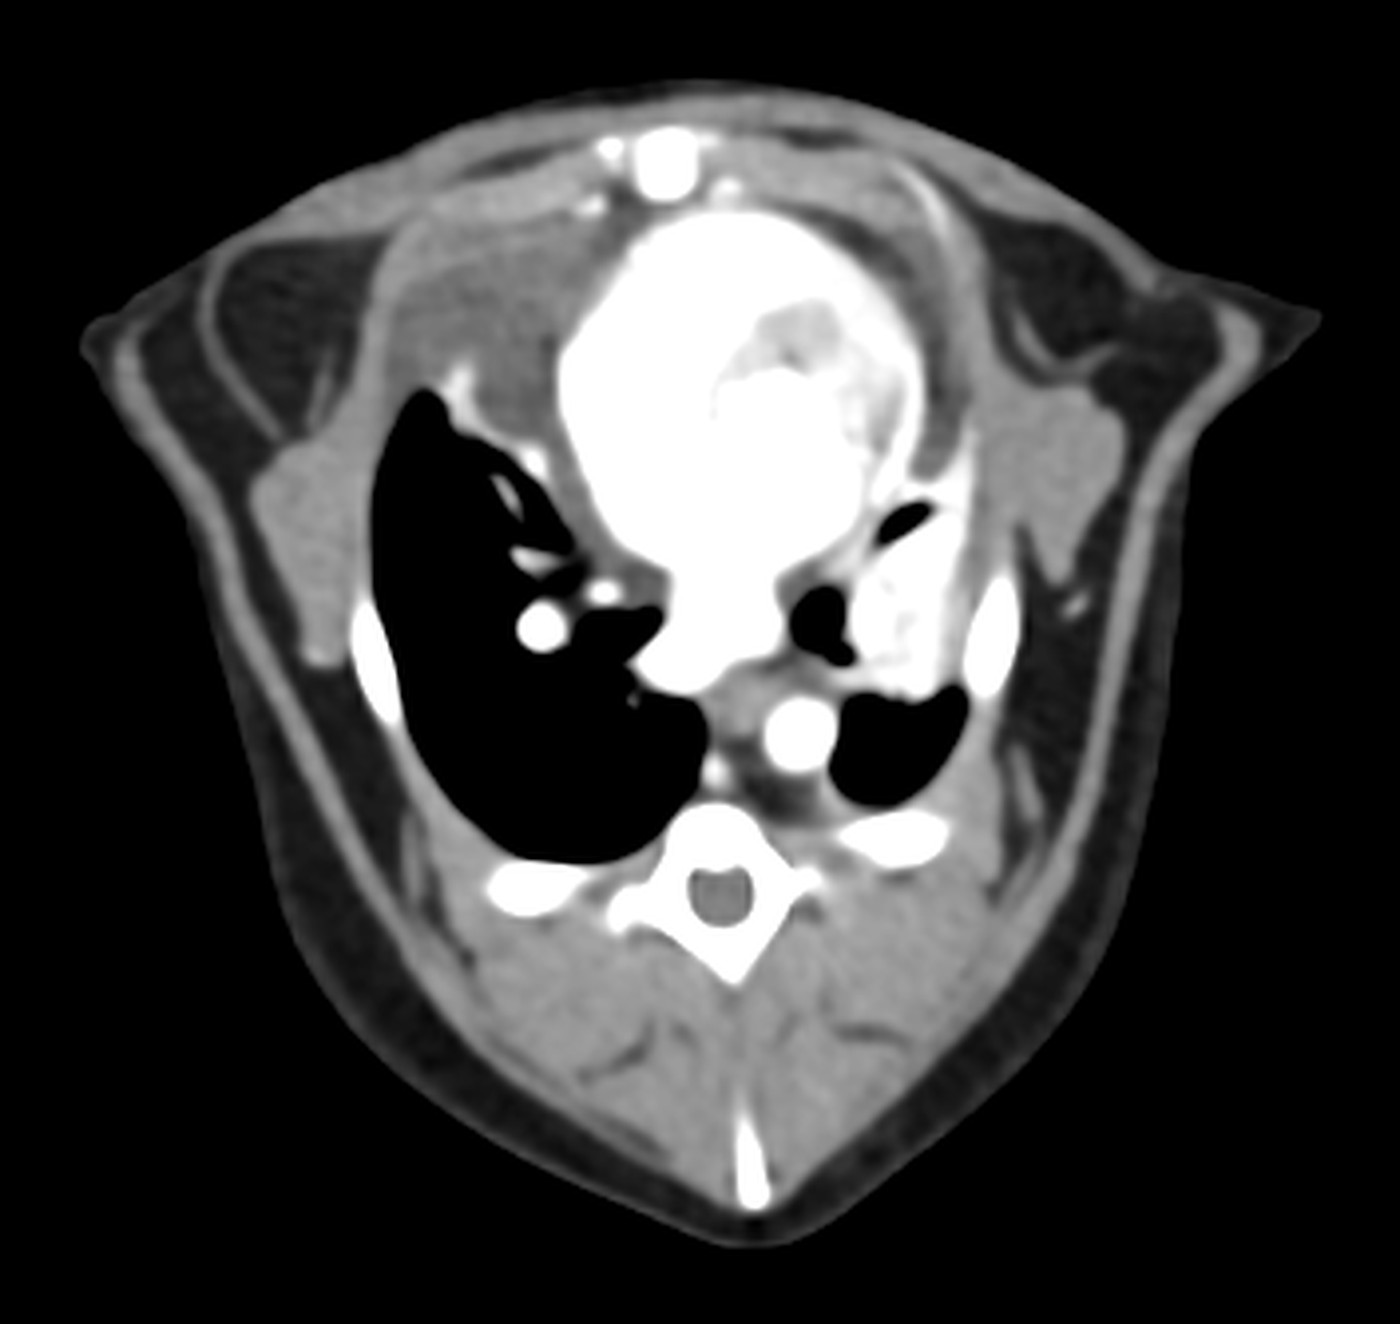
Transverse slice through the thorax, post-contrast, W 400 / L 40: bilateral pleural effusion, lobar atelectasis.
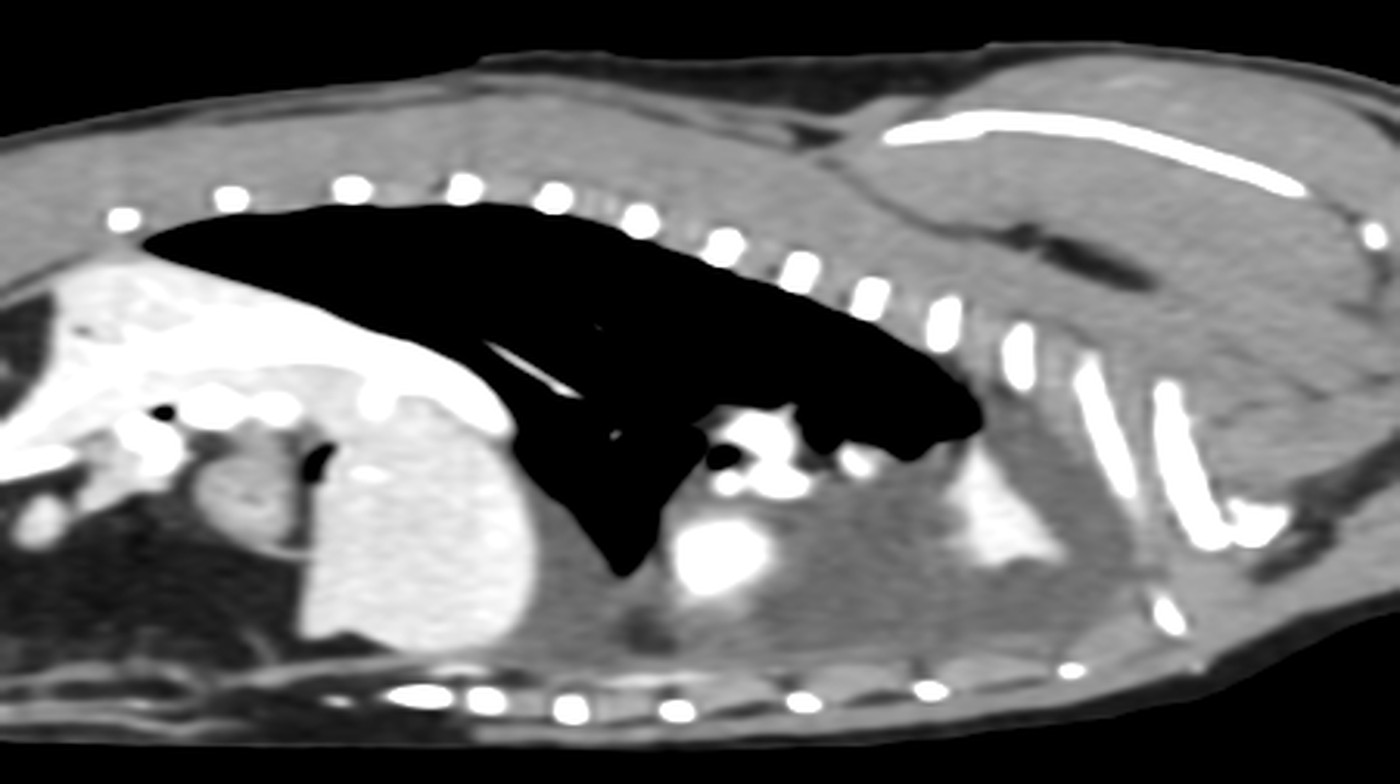
Sagittal plane through the thorax, post-contrast, W 400 / L 40: pleural effusion and collapsed lung lobes.
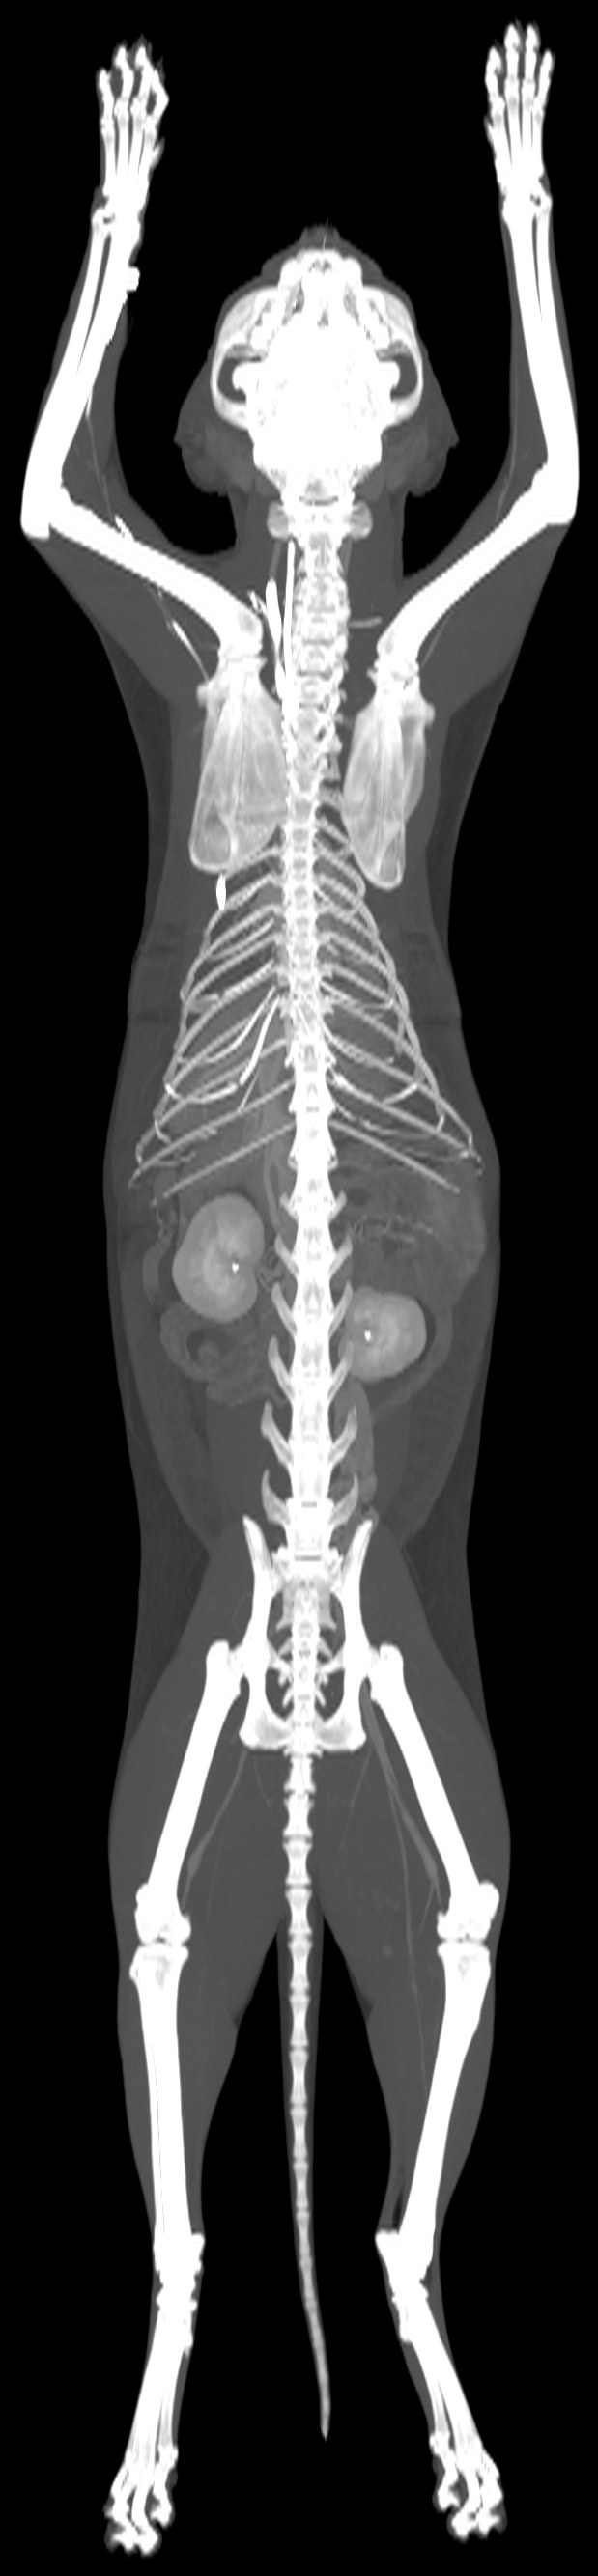
Dorsal MIP of the entire volume, post-contrast.
History
Excision of a thigh mass 2 months previously (adenocarcinoma). Laparotomy for suspected diaphragmatic hernia 5 days before CT. Currently tachypnoea, abdominal breathing, muffled heart sounds and elevated renal parameters. Approximately 100 ml of chylous fluid drained from the thoracic cavity before CT.
Technique
4,433 slices (1 and 2 mm), pre- and post-contrast series reconstructed with medium- and high-frequency algorithms. Good study quality.
Findings
–Lungs: right cranial and right middle lobes, both the cranial and caudal parts of the left cranial lobe, and the accessory lobe consolidated with reduced volume and air-filled lobar bronchi; caudal lobes aerated.
–Pleura: fluid in both pleural spaces; multifocal thickening of the visceral pleura, without nodules or masses.
–Lymph nodes: enlarged cranial mediastinal nodes (irregular, spherical, heterogeneously enhancing) and mildly enlarged sternal nodes; enlarged left popliteal node.
–Adrenal glands: symmetrically enlarged (DV right 5.2 mm, left 5.1 mm), with normal shape and enhancement and no vascular invasion.
–Kidneys: mild multifocal surface indentations at the poles; small bilateral mineralisations in the renal pelves.
–Muscles: bilateral asymmetrical thickening of the hypaxial musculature at the level of L7 and the sacrum, in the location of the psoas minor muscles, heterogeneously enhancing, without vascular invasion; focal heterogeneous enhancement of the soft tissues dorsomedial to the body of the right ilium.
–Peritoneum: multiple small gas bubbles and diffuse mild fat stranding.
Conclusion
–Bilateral pleural effusion.
–Atelectasis of several lung lobes, most likely secondary to the effusion.
Ventral thoracic wall mass with probable invasion of the deep pectoral muscle; suspected ectopic ureters
Patient
cat, Maine Coon, male, 10 years
Examination
CT of the thorax, abdomen and pelvis, pre- and post-contrast
Date
June 2026
Volume rendering (VR) with an HU-based colour map from the 2 mm post-contrast series (late venous phase), resampled to an isotropic voxel size of 0.4 mm, right lateral view: ventral thoracic wall mass at the level of the cranial sternebrae; kidneys and liver post-contrast.
Transverse slice at the level of the cranial sternebrae, post-contrast, W 400 / L 40: heterogeneously enhancing ventral thoracic wall mass.
Midsagittal plane, post-contrast, W 400 / L 40: ventral thoracic wall mass at the level of the cranial sternebrae.
Dorsal MIP of the entire volume, post-contrast.
History
Mass on the ventral thoracic wall adjacent to the sternum.
Technique
2,457 slices (1 and 2 mm), pre- and post-contrast series reconstructed with medium- and high-frequency algorithms; 2 post-contrast series in the late venous and excretory phases. Good study quality; motion artefacts in the lungs.
Findings
–Thoracic wall: spherical, heterogeneously enhancing mass of soft tissue attenuation in the subcutis of the ventral thoracic wall at the level of sternebrae 1–3 (49.5 × 22.8 × 35.6 mm); focal invasion of the left deep pectoral muscle in the median plane cannot be excluded; very close contact with the right deep pectoral muscle; no invasion of the thoracic cavity or pleural spaces.
–Lungs: right middle lobe and caudal part of the left cranial lobe with reduced volume and consolidation, air-filled lobar bronchi; remaining lobes difficult to assess owing to motion artefacts.
–Heart: dilatation of the left atrium and left ventricle.
–Kidneys and ureters: right kidney small, with irregular contours and heterogeneous enhancement; left kidney unremarkable; focal dilatation of the left ureter in its proximal third; exact site of insertion of both ureters not identified; urinary bladder distended, containing a very small amount of contrast medium; urethra filled with contrast medium.
Conclusion
–Ventral thoracic wall mass, very likely with focal invasion of the left deep pectoral muscle. Most likely neoplasia (suspected sarcoma).
–Right-sided nephropathy.
–Focal left hydroureter.
–Very likely ectopic insertion of both ureters into the proximal urethra.
Recommendation
Biopsy and correlation with cytology or histopathology. Ultrasound of the urinary tract. To confirm or rule out ectopic ureters, repeat CT (excretory CT urography) after an enema and with an appropriately filled urinary bladder (avoiding both overdistension and complete emptying).
Translated from the Czech original, with identifying details removed. Report signed by MVDr. Ladislav Stehlík, Ph.D..
Oncological staging of a soft tissue sarcoma of the pelvic region
Patient
dog, mixed breed, spayed female, 11 years
Examination
Whole-body CT, pre- and post-contrast
Date
August 2026
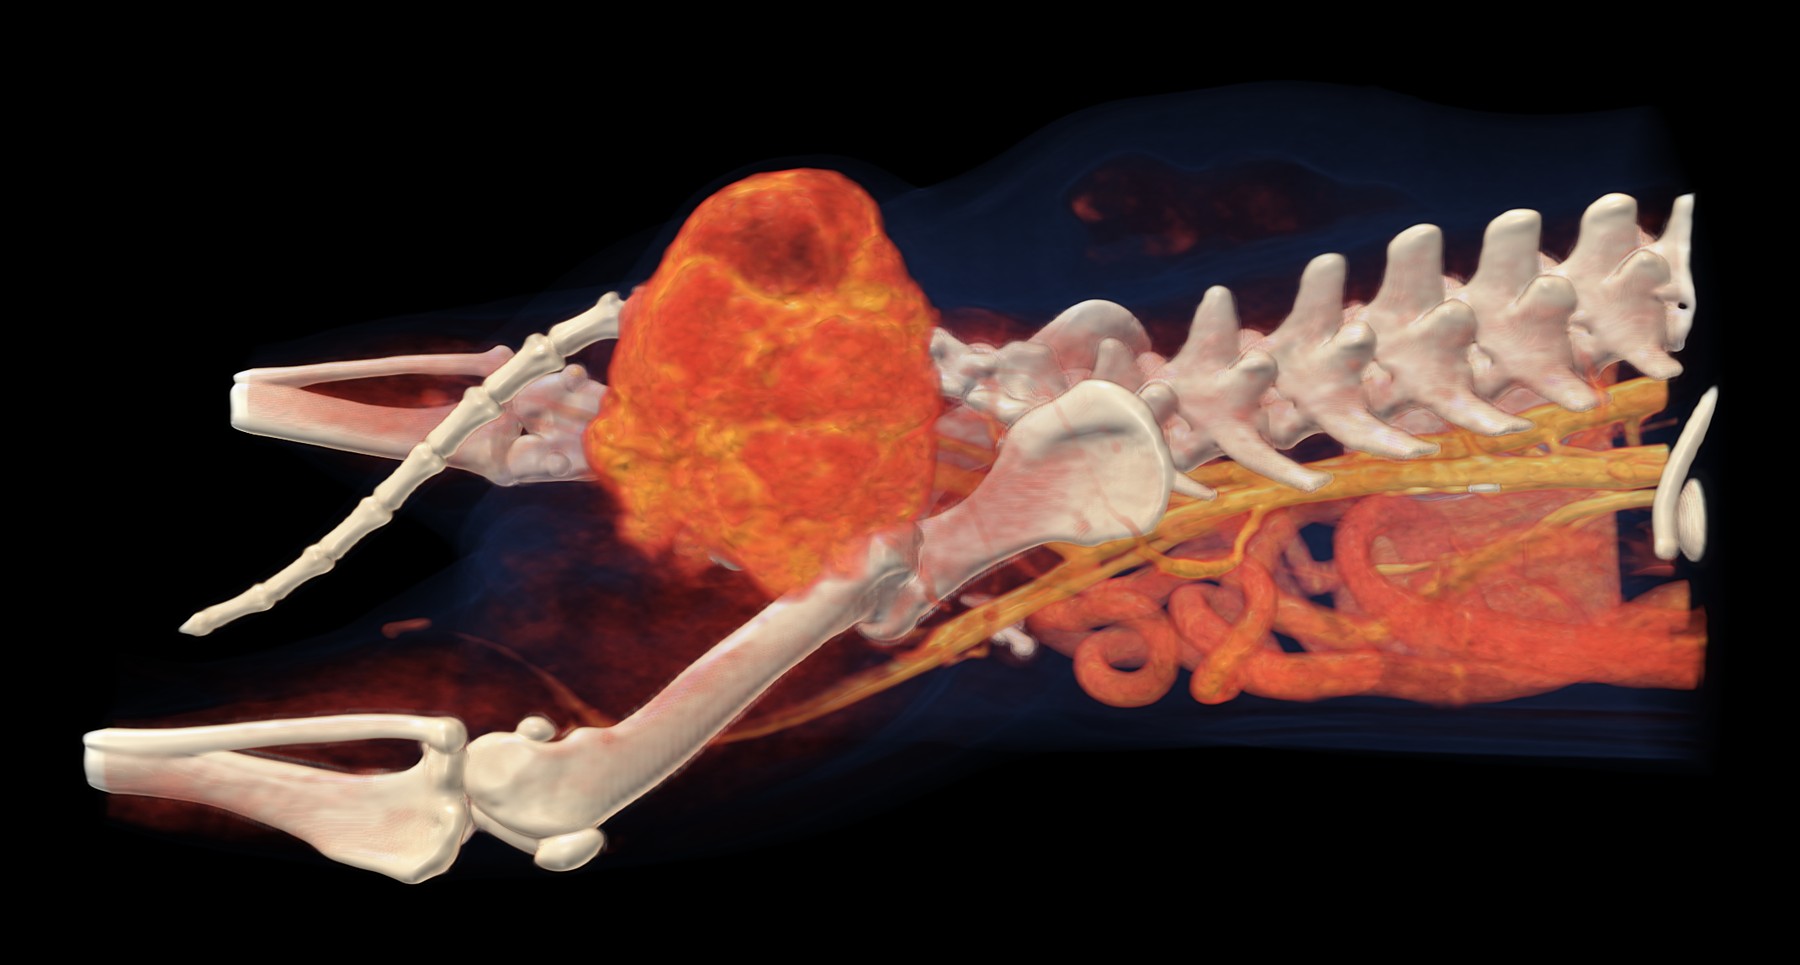
Volume rendering (VR) with an HU-based colour map from the 2 mm post-contrast series, resampled to an isotropic voxel size of 0.4 mm, pelvic and lumbar region, right lateral view: multilobular mass dorsal to the right hip joint, aorta and iliac arteries; a second mass shows through in the contralateral lumbar region.
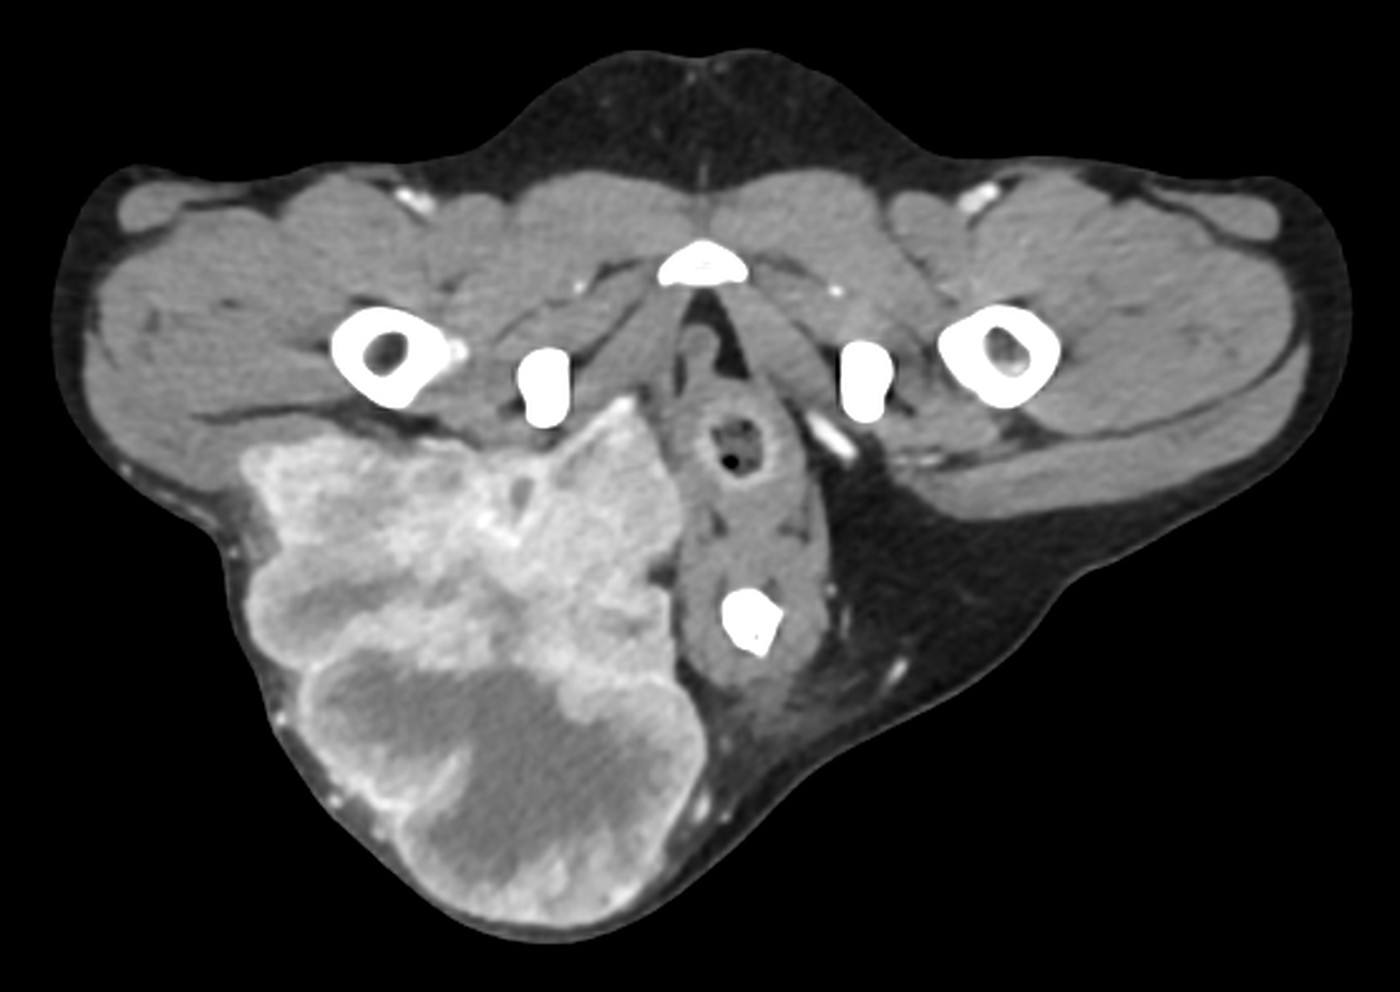
Transverse slice at the level of the hip joints, post-contrast, W 400 / L 40: multilobular, heterogeneously enhancing mass dorsally on the right, with displacement of the rectum to the left.
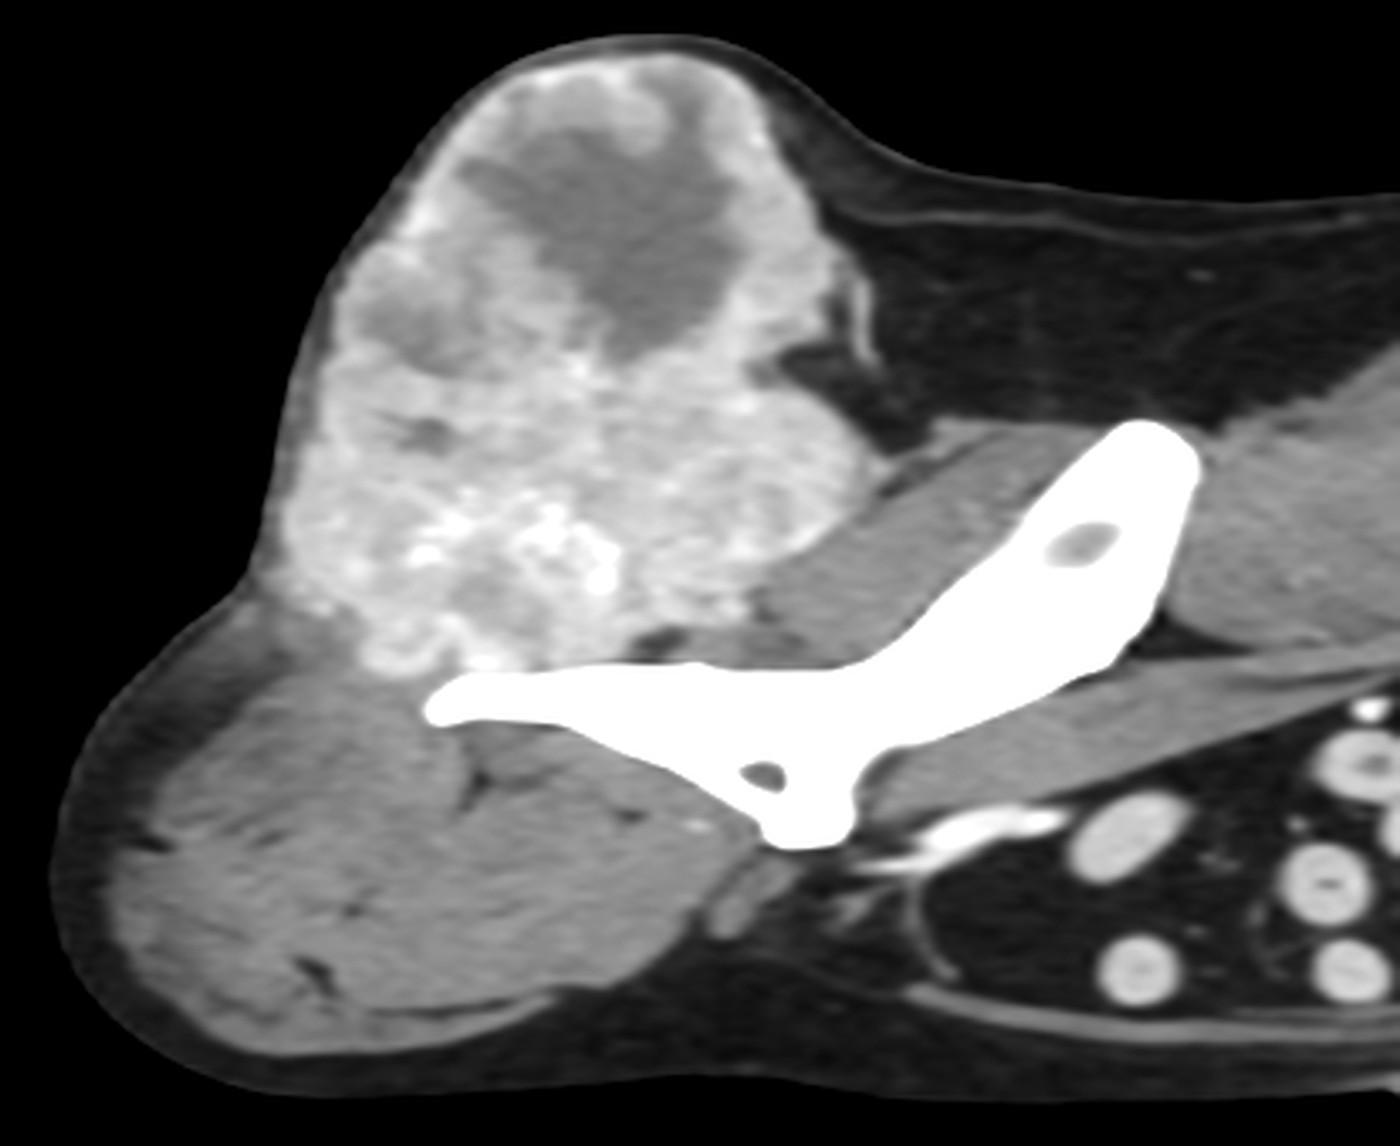
Parasagittal plane through the mass on the right, post-contrast, W 400 / L 40: multilobular, heterogeneously enhancing mass dorsal to the right hip joint.
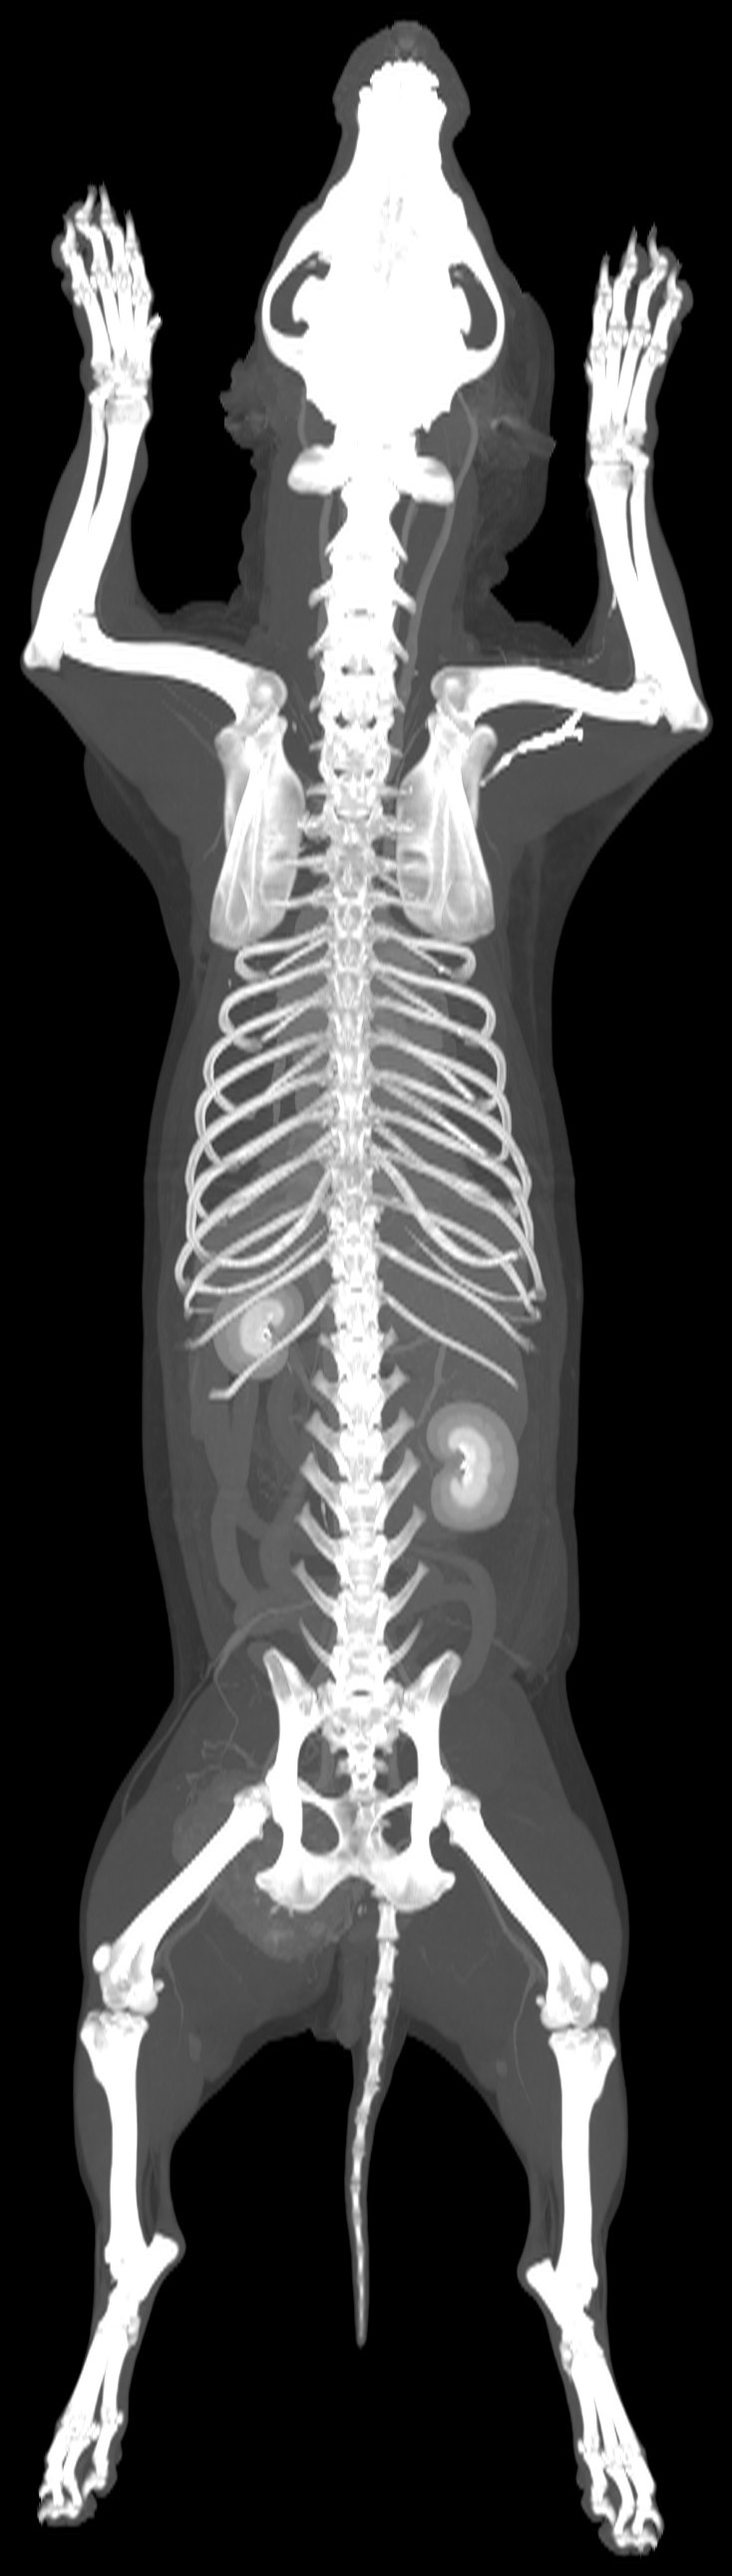
Dorsal MIP of the entire volume, post-contrast.
History
Mass at the level of the pelvis on the right; biopsy result: soft tissue sarcoma. Oncological screening.
Technique
3,438 slices (1 and 2 mm), pre- and post-contrast series reconstructed with medium- and high-frequency algorithms; 1 post-contrast series in the late venous phase. Excellent study quality.
Findings
–Pelvis: multilobular mass of soft tissue attenuation with central mineralisation, heterogeneously enhancing and well defined, located dorsally at the level of the right hip joint (69 × 69 × 64.5 mm); invasion of the right gluteal musculature, with suspected invasion also of the right piriformis, biceps femoris and semitendinosus muscles; extends into the pelvic cavity from the right dorsal aspect; mild compression and displacement of the rectum to the left; adjacent bone unremarkable.
–Left lumbar region: irregular, elongated mass of soft tissue attenuation with heterogeneous enhancement, located subfascially within the fat from the level of L5 to the wing of the ilium (68 × 20 × 51 mm), well defined.
–Lungs: multiple miliary mineralised nodules, predominantly subpleural; small thin-walled, air-filled lesion in the right caudal lobe (d = 6 mm).
–Anal sacs: subtle mineralised sediment (sacculoliths); mild compression of the right anal sac due to the mass effect.
Conclusion
–Multilobular expansile and invasive mass at the level of the right side of the pelvis, consistent with neoplasia, most likely sarcoma.
dog, Jack Russell Terrier, spayed female, 10 years
Examination
Whole-body CT, pre- and post-contrast
Date
May 2026
Volume rendering (VR) with an HU-based colour map from the 2 mm post-contrast series, resampled to an isotropic voxel size of 0.4 mm, left lateral view. The lymphadenopathy and subcutaneous masses are assessed on the cross-sectional images.
Transverse slice through the cranial abdomen, post-contrast, W 400 / L 40: hepatomegaly, plaque-like subcutaneous masses dorsally.
Dorsal plane through the trunk, post-contrast, W 400 / L 40: subcutaneous thoracic wall mass.
Dorsal MIP of the entire volume, post-contrast.
History
Gastrointestinal signs for approximately one year. Currently generalised lymphadenopathy, hyperthermia and a large subcutaneous mass on the right side of the thorax.
Technique
3,159 slices (1 and 2 mm), pre- and post-contrast series reconstructed with medium- and high-frequency algorithms; 2 post-contrast series in the late venous phase. Excellent study quality.
Findings
–Lymph nodes: enlarged, without a visible hilum, homogeneous; mandibular, parotid and medial retropharyngeal bilaterally, superficial and deep cervical, sternal, cranial mediastinal, axillary, iliosacral, superficial inguinal and popliteal bilaterally.
–Subcutis and superficial fascia of the thoracic and abdominal walls: multifocal thickening ranging to plaque-like masses of soft tissue attenuation with homogeneous enhancement, bilaterally and dorsally, well defined, without intermuscular spread; the largest is dorsolateral on the right, extending from T6 to L3–4.
–Thymus: enlarged, homogeneously enhancing.
–Liver and spleen: diffusely enlarged, homogeneously enhancing, with smooth margins.
–Brain: asymmetry of the lateral ventricles (right > left).
Conclusion
–Generalised lymphadenopathy.
–Bilateral subcutaneous masses of the thoracic and abdominal walls.
–Most likely DDx: lymphoma, disseminated histiocytic sarcoma, reactive histiocytosis; among infectious diseases, Leishmania sp. (travel to or residence in an endemic area must be confirmed).
Recommendation
Biopsy and correlation with cytology or histopathology, with additional specialised tests where appropriate (Leishmania PCR, PARR, immunohistochemistry).
Translated from the Czech original, with identifying details removed. Report signed by MVDr. Ladislav Stehlík, Ph.D..
3,223 slices (1 and 2 mm), pre- and post-contrast series reconstructed with medium- and high-frequency algorithms; 3 post-contrast series in the late venous phase. Diagnostic study quality; motion artefacts in the lungs.
Findings
–Lungs: multiple small nodules of soft tissue attenuation, both central and subpleural, spherical and irregular, some poorly defined (halo sign).
–Mediastinum: small structure of metallic attenuation with marked artefacts, dorsal to the oesophagus and ventral to the aorta; oesophageal lumen unremarkable.
–Lymph nodes: enlarged cranial mediastinal, sternal, hepatic, gastric, splenic, jejunal and lumbar aortic nodes, without a visible hilum.
–Heart: dilatation of both atria and both ventricles.
–Liver: diffusely enlarged, with rounded margins, multifocal heterogeneous enhancement and a periportal halo. Gallbladder distended, with a hyperattenuating peripheral rim of irregular width and a small amount of mineralised sediment.
–Spleen not visualised (previous splenectomy).
–Kidneys: both enlarged, irregular in shape and heterogeneously enhancing, with multiple parenchymal nodules to masses of soft tissue attenuation, homogeneously enhancing, hypoattenuating relative to the cortex and protruding beyond the renal contour.
–Ureters: left ureter unremarkable, with normal filling; right ureter multifocally thickened and heterogeneously enhancing, with no contrast filling in any of the post-contrast series.
–Peritoneum: multifocal small volumes of free fluid and fat stranding.
Conclusion
–Multifocal lymphadenopathy, most likely neoplastic. DDx: reactive.
–Hepatopathy, nephropathy, right ureteral thickening; the most likely common cause is lymphoma.
–Pulmonary nodules consistent with metastases.
–Cholecystopathy. DDx: chronic cholecystitis, lymphoma, other neoplasia.
–Peritonitis.
–Generalised cardiomegaly.
Recommendation
Biopsy and correlation with cytology or histopathology.
Translated from the Czech original, with identifying details removed. Report signed by MVDr. Ladislav Stehlík, Ph.D..
Hepatosplenomegaly, multifocal lymphadenopathy and pneumonia in an anaemic dog
Patient
dog, German Shepherd Dog, spayed female, 11 years
Examination
CT of the neck, thorax, abdomen and pelvis, pre- and post-contrast
Date
August 2026
History
Dyspnoea, lethargy, anaemia.
Technique
4,010 slices (1 and 2 mm), pre- and post-contrast series reconstructed with medium- and high-frequency algorithms; 3 post-contrast series in the late venous and excretory phases. Diagnostic study quality; motion artefacts.
Findings
–Neck: enlarged left superficial cervical lymph node, without a visible hilum, with homogeneous enhancement.
–Lungs: multiple miliary and small nodules of soft tissue attenuation, diffusely distributed; consolidation of the ventral third of the right cranial lobe and of the cranial part of the left cranial lobe with air bronchograms; in the remaining lobes, ground-glass opacities ranging to consolidation with a diffuse distribution.
–Thoracic lymph nodes: enlarged left axillary, sternal, one cranial mediastinal and the tracheobronchial nodes, without a visible hilum, some with heterogeneous enhancement.
–Liver and gallbladder: diffuse hepatomegaly with rounded, smooth margins; thickened gallbladder wall with a peripheral rim of fluid attenuation (‘sandwich’ appearance); mineralised sediment.
–Spleen: diffuse splenomegaly with homogeneous enhancement.
–Abdominal lymph nodes: enlarged hepatic (spherical), splenic, lumbar aortic and medial iliac nodes, with heterogeneous enhancement.
–Peritoneum: multifocal free fluid.
–Skeleton: bilateral osteoproliferation of the femoral heads and acetabula; multiple osteoproliferations of the lumbar vertebral bodies, with narrowing of the right neuroforamen at L7–S1.
Conclusion
–Diffuse hepatomegaly and splenomegaly, multifocal lymphadenopathy. DDx: lymphoma, systemic infection, extramedullary haematopoiesis (the splenomegaly alone may also be secondary to the anaemia).
–Gallbladder wall thickening consistent with oedema. DDx: anaphylaxis, cholecystitis, hypoalbuminaemia.
–Small-volume ascites. DDx: neoplastic, secondary to hepatopathy.
–Pulmonary consolidation with this distribution is most consistent with pneumonia.
–Pulmonary ground-glass opacities. DDx: lymphoma, interstitial pneumopathy, pneumonia; they may also result from motion artefacts or anaesthesia.
Incidental findings
–Spondylosis deformans.
–Degenerative lumbosacral stenosis (DLSS).
Recommendation
Biopsy and correlation with cytology or histopathology.
Translated from the Czech original, with identifying details removed. Report signed by MVDr. Ladislav Stehlík, Ph.D..